




Mental health
Short-term bets, long-term needs: Rethinking investment in women’s health


Short-term bets, long-term needs: Rethinking investment in women’s health
By Morgan Rose, CNM, WHNP-BC, IBCLC | Chief Science Officer, Ema
Most investors treat women’s health as a series of disconnected markets. One fund backs cycle tracking. Another backs a postpartum platform. A third takes a bet on menopause.
While women experience distinct life stages, they progress through them in a continuous and interconnected way. A fertility journey may follow years of hormonal birth control.
Postpartum mental health may trigger a return of PMDD. Perimenopause may intensify autoimmune symptoms that a woman’s been tracking since adolescence. It’s all one story.
The system just isn’t built to integrate it.
This is how women end up using three separate apps with three different symptom logs, none of which communicate with each other. They repeat themselves to the system over and over.
Their data is siloed. Their emotional context is lost. Their trust in digital health wears thin.
And that’s more than a user experience problem; it’s a clinical one. Tech built and funded to support women must be designed with that reality in mind.
At Ema, we built the first agentic AI layer, purpose-built for women’s health, designed to understand her history, hormonal shifts, emotional context, and clinical risk in real-time.
It’s more than conversation. It’s care that connects.
Our AI supports users across fertility, postpartum, and menopause, treating these life stages as interconnected rather than isolated experiences.
But the real value lies in backing AI that connects, adapts, and scales with her across life stages, from puberty to postmenopause.
And we’ve raised over $3M from investors like Emmeline Ventures, Kubera Venture Capital, Hearst Labs, Acumen America, and Techstars to prove there is an investor market for longitudinal and connected care.
Why AI Is Not Just Another Point Solution
The opportunity lies in building AI that carries memory, recognises emotional and hormonal patterns, and supports women through years of shifting health needs, not just to accelerate answers, but to sustain care and improve health outcomes.
Women don’t need 10 tools for 10 life stages. They need one layer of intelligence that knows their history and evolves with them.
That requires AI trained on longitudinal, women-centered data.
It means remembering the postpartum depression that followed a second child, the cycle shifts after an IUD change, and the miscarriage before a new fertility journey.
Naseem Sayani is Director of the Innovator’s Circle at Women’s Health Access Matters, Operating Advisor at How Women Invest, and Advisor at Tower Capital.
She said: “The opportunity at the intersection of women’s health and AI is not just about smarter in-the-moment insights – we’re talking about more advanced everyday care, and an industry wide transformation from anecdote-based care to actual data-based care.
“Small models will become more important than large models, and with higher investment in these innovations, we can enable a Black mom in California avoid preeclampsia; a South Asian teenage girl in New Jersey understand her culture’s predisposition for endometriosis; and a Caucasian woman in Missouri chose birth control that helps her avoid her family’s history of cardiac disease.
“This interconnected healthcare transformation is at our fingertips.”
Investing in AI for women’s health is how we finally build continuity into a system that’s been fractured for too long.
The Silo Problem: Funding Symptoms, Not Systems
AI in healthcare is booming. The market is projected to hit $431 billion by 2032, driven by LLMs, workflow automation, and AI-first platforms.
Meanwhile, investment in women’s health hit a record $2.6 billion in 2024, and up to $10.7 billion when you include conditions that disproportionately affect women, from autoimmune disease to chronic fatigue.
So why is so little capital flowing to the intersection of AI and women’s health?
Because most AI funders still look for large, generalisable models. And most women’s health funders are still thinking in point solutions.
Very few are investing in vertically integrated AI designed to understand complex, longitudinal, and emotionally nuanced care.
The short-term thinking that drives product silos also shapes where capital flows. Investors back tools that solve for isolated needs, in isolated moments, without asking how those tools will connect, carry forward context, or scale with a woman’s life.
And nowhere is that pattern more evident than in the current landscape of AI investment.
A Call to Investors
If you’re funding the next wave of women’s health innovation, ask what it’s built on.
If the product doesn’t carry memory, adapt to complexity, or unify care across her lifespan, then it’s not future-proof. Let others chase features. Let’s build the foundation they’ll all need to run on.
Ema is raising now. Let’s talk if you’re ready to build what lasts.















AI-powered journaling app Véa is supporting mental health by helping women to understand their thoughts, triggers and behavioural patterns.
Winner of the Brain and Mental Health Innovation Award at this year’s Femtech World Awards, Véa is designed to address the emotional gap in women’s health technology.
The journal – which has been built by a female team and trained on women’s health papers – tracks inner states, provides personalised insights and somatic practices, and utilises AI to explain complex neuroscience in relatable terms.
Described by its founders as a “protector, seeker, and sculptor”, Véa provides a longitudinal map of women’s emotional journeys, integrating journaling with therapy and both in-person and online community support.
The journal’s goal is to improve women’s mental health without replacing professional care.
Zahra Bhatti, co-founder and CEO and Katrina Zalcmane , co-founder and growth lead speak to Femtech World about the technology, winning a Femtech World Award and their plans for the future.
Women’s health and wellbeing technology has grown so rapidly over the last few years, but is largely focused around physical health. What was the emotional gap that you saw that inspired you to create the journal?
“Women’s health has been focused on reproductive health and physical health, but it is all one ecosystem – it always starts with the mind,” says Zahra.
“Whatever you feel down here, you feel up there too, and the hormones reflect that.
“With Véa, it was actually built from our own personal experience of burnout.
“We wanted to make a space where women could feel safe and were able to reflect what’s on their mind, but also understand their mind the same way that women understand their hormones.
“Women need to understand what happens in our minds. Véa helps women to understand cognitive distortions, why they feel the way they feel, black and white thinking – we wanted to really surface that for them.
“For example, when you’re in your luteal phase, your serotonin levels drop, so that means you’re going to be a bit more nervous.
“You’re going to be more reactive. You’re going to be taking things more deeply, and that’s something that your rational mind wouldn’t normally do if you’re in your ovulation phase.
“So that’s what Véa does – she reflects that back to you, so you understand your body and thought processes.”
Véa describes itself as a journal that’s designed for the female mind. What does that mean in practice, and how does the experience differ from using traditional journaling?
“The majority of our team is female, so Véa has been built from all of our lived experiences, and the AI itself is trained on women’s health papers,” says Katrina.
“It takes into account what having a certain condition means for individuals. For example, if you have endometriosis or PCOS, We’ve trained our AI on womens health data and research, which gets reflected back to the woman in a simple and effective way
“We have a clinical board, who are all also women, who look through the AI and the language. They ensure that all outputs are evidence based, ethical and take into account the various therapies which are proven to work for women.
“We also have somatic practices which are focused on women which we call “rituals”. We have a self-inquiry ritual, a confidence mirror ritual, or we have one of our psychotherapists on the board who does therapy through novels, for example.
“These aim to make you the protagonist of your story.
“Generic journaling apps are one size fits all, but women are not one size fits all, and that’s what we’ve made sure to put in the forefront of Véa.”
Instead of conventional mood tracking, you are focused on the inner states of women. How do you develop that approach, and what kind of insights has it revealed about how women reflect on their emotions?
Katrina says: “Mood plays a part in our inner state and Véa checks in on that.
“It allows you to have a journey across time. For example, on a good day, maybe their “protector” aspect is good at setting boundaries, but on a bad day, it could be really closed off.
“It’s a richer approach, and these inner states are tied to specific prompts which are then linked in the journaling.”
“As women, we are fluid,” adds Zahra.
“We are not one entity.
“For example, you might be in a state where you’re really overthinking, but actually, you’re seeking new perspectives, and that’s why within Véa, the inner state is called a “seeker”.
“When you converse with Véa in your seeker mode, she will challenge you in a Socratic way.
“However, the next day, you might be a “protector”, and then Véa will adjust her voice for a reflective and exploratory tone compared to when you were a seeker.
“Another state which I love is the “sculptor” which is when you’re feeling confident.
“When you’re a sculptor, Véa will talk about how you can be creative, asking questions such as ‘what did you create today?’ ‘How did that make you feel?’ and ‘How would you describe that if you could put a shape to this color, this feeling?’, for example.
“Véa goes into all of these different modes, and it builds a longitudinal map of the woman as well. So, throughout weeks, months and years, you can see how you’ve changed across time.”
How did you approach designing an AI companion that feels supportive without replacing human connection or professional care?
“For the past six years, I’ve been a product manager. So I’ve seen how all of these web apps and applications have been built, and I’ve worked quite deeply with AI so I knew what was missing and like what women truly needed,” says Zahra.
“The key thing for us is that we want to bring “URL to IRL” [in real life].
“We have a community that goes alongside Véa. This includes a WhatsApp community and events.
“We turn the rituals inside Véa into in-person workshops at our events with our clinical board and with professionals in the space.
“We are not neuroscientists, but there are neuroscientists who have helped us build the app, and we make sure that AI is there to support you, but AI will never replace that human touch.
“That’s something that’s very close to us, and we want to make sure we connect people together and help people reflect in a safe space.
“As well as AI, there is the option to talk to the clinical board, to use their rituals, to reflect with the community, and go to our events.”
Katrina adds: “The key is that whatever the touch point is, whether it’s the app or it is an event or even our online community, we don’t want women to feel alone. We want them to feel together, grow together, and process together.”
People may often start journaling with good intentions, but struggle to stick with the practice. What have you learned about building habits and how those insights have shaped the experience of your product?
Zahra says: “I think everyone wants to gamify things – what helps us is the community aspect.
“We’ve created a tribe through the community, and because it’s so hyper personalised, you help shape the app, the app doesn’t shape you. You have full control, which makes people want to come back.
“Véa remembers what you said yesterday as well as six weeks ago, and she will surface that.
“We do have “streaks”, but our streaks are very gentle – every time you get a streak, you get a neuroscience fact along with it.
“Something else we have built in that helps retention is “breakthroughs”. When Véa detects a shift in language, and will highlight, for example, that you have shifted from overthinking to certainty.”
“I think people are sick of data, they’re sick of data that they can’t interpret from. Véa interprets for you.
“Soon we will evolve even more and add more features such as cycle tracking, wearable tracking and hormone tracking, to build out that ecosystem.”
What does success look like for Véa and how do you see the app and the community evolving as you move forward?
“We want to launch across so many different markets. Our next target is the US,” explains Katrina.
“We want to bring our events over there as well. We do a lot of corporate events too. We have one with NatWest coming up – we know that work stress is a big thing, especially amongst females.
“I think there’s a real space for that in the corporate world, so that’s one of our key focuses.”
Zahra adds: “Growing in markets and keeping going with our communities. We have just launched a supper club which sold out in three days in Manchester, which is absolutely amazing. We’re doing some in London and Amsterdam as well in the next few months. We are focused on growth, growing our board as well, and keeping the female mind at the center.”
What does it mean to win the Femtech World Award?
Katrina says: “When you are so passionate and truly believe in something, you do it for that reason, but that external validation of seeing that it also matters for others in the wider space means so much.
“Especially, in Femtech – it is a whole category that has been growing, but when it comes to funding and recognising women’s issues, there is still a lot of awareness that needs to be raised.
“Being recognised gives us that fuel to continue and drive forward, and that it really does matter.”
“We want to be at the forefront of women’s mental wellness as a whole, and have put many sleepless nights into developing the app, so it is a big testament to that,” adds Zahra.


Women entering pregnancy with multiple long-term health conditions face higher risks of miscarriage and other complications, a UK study found.
Those with two or more pre-existing physical or mental health conditions had a 20 per cent higher risk of miscarriage than women with no long-term conditions.
They also had more than twice the risk of venous thromboembolism and around four times the risk of antenatal anxiety and depression.

The UK-wide research team analysed 2,225,701 pregnancies and birth events recorded between 2000 and 2022 across five datasets covering England, Scotland, Wales and Northern Ireland.
Women with multiple long-term conditions had a 69 per cent higher risk of nausea and vomiting during pregnancy and a 42 per cent higher risk of pre-eclampsia.
The women also had a 32 per cent higher risk of placental abruption and a 26 per cent higher risk of gestational diabetes.
Risks rose as the number of existing conditions increased.
Among women with three or more long-term conditions, the risk of venous thromboembolism was more than three-and-a-half times that of women with no long-term conditions.
Researchers said the findings had implications for maternity services, where care pathways are largely centred on individual conditions and may not adequately meet the needs of women with multiple long-term conditions.
Dr Kelly-Ann Eastwood, joint senior author and honorary lecturer at Queen’s University Belfast and consultant obstetrician at St Michael’s Hospital, Bristol NHS Foundation Trust, said the results “help define” the urgent clinical challenges facing women entering pregnancy with multiple long-term conditions and the clinicians caring for them across the UK.
“These findings highlight the pressing need to restructure existing maternity services to improve antenatal outcomes,” she added.
The authors cautioned that the study was observational and relied on routinely collected health records, meaning some conditions and outcomes may have been under-recorded, while residual confounding could not be excluded.
The researchers plan to examine birth and child outcomes and identify which combinations of long-term conditions carry the greatest risk.

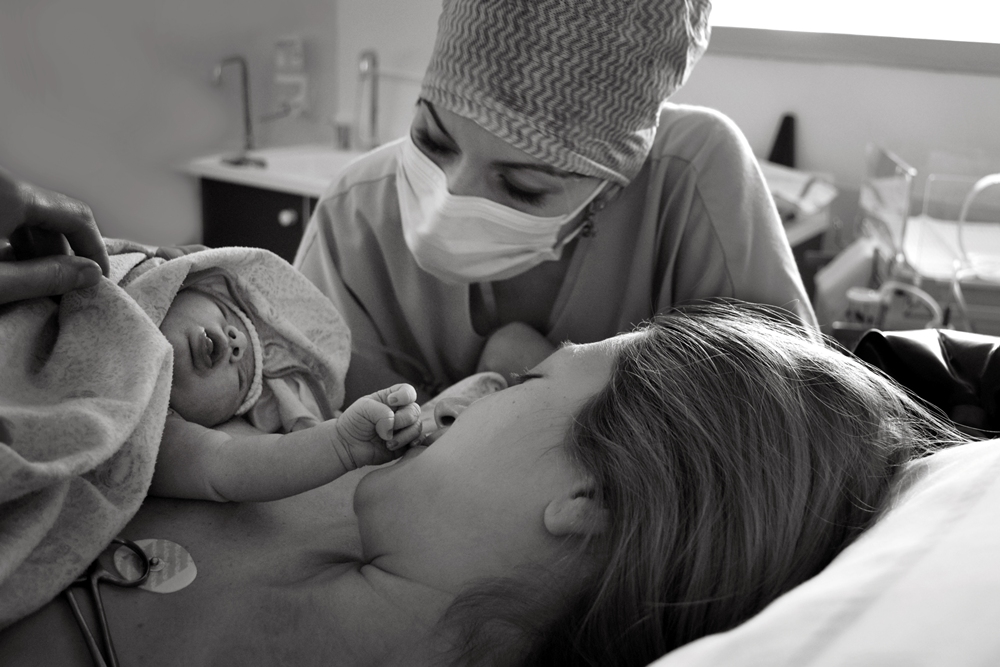
Women with childbirth-related PTSD had healthcare costs 2.5 times higher than women without PTSD from six to 12 months after birth, a report found.
The analysis estimated that early prevention of traumatic births and childbirth-related post-traumatic stress disorder (PTSD) could save the NHS around £26m each year.
Women with PTSD were also less likely to have returned to work by 12 months after giving birth, suggesting potential longer-term employment and economic effects.
The report from City St George’s, University of London was launched at an All-Party Parliamentary Group (APPG) on Birth Trauma event on 10 September 2026.
Researchers calculated the potential NHS savings using the number of births reported in NHS hospitals in 2024-25 and the UK prevalence of childbirth-related PTSD.
Around one in 20 women in the UK develop PTSD following childbirth, while recent research has shown that the condition remains underdiagnosed.
The findings draw on research that tracked more than 2,000 women in England and Scotland from pregnancy to two years after birth. Researchers assessed mental health, use of health services and employment outcomes.
The research included assessments of childbirth-related PTSD and PTSD arising from other traumatic experiences. It also included a separate Birth Trauma Association survey examining women’s experiences of birth trauma.
Between six and 12 months after birth, healthcare and support service costs for women with childbirth-related PTSD were 2.5 times those of women without PTSD.
Women with low or moderate symptoms, including those reporting one or two PTSD symptoms, also had higher healthcare service costs than women without PTSD.
Just over half, 53 per cent, of women with PTSD had returned to work by 12 months after giving birth, compared with 68 per cent of women without symptoms.
Women with PTSD were more likely to be referred for mental health support, but more than half received no referral.
Those whose PTSD followed a traumatic birth also had slightly higher healthcare costs than women whose PTSD resulted from other traumatic experiences.
The researchers called for routine PTSD assessment and treatment during pregnancy and after childbirth, alongside greater access to specialist perinatal mental health services.
They also recommended training healthcare staff in perinatal trauma, trauma-informed care and identifying women at risk of PTSD.
The report said further research was needed to establish whether screening, treatments and trauma-informed care pathways are effective and evidence based.
The work follows the APPG’s 2024 Birth Trauma Inquiry, which highlighted the effects of birth trauma on women and families and called for evidence on its wider public health and societal costs.
The report focused primarily on healthcare use and did not attempt to calculate all costs associated with birth trauma and postnatal PTSD, including wider employment, family and societal effects.










 Menopause5 days ago
Menopause may not explain rising heart condition in women – study

 Fertility1 week ago
Paracetamol use may impact future fertility, studies suggest

 Events2 weeks ago
Last chance to save on Women’s Health Week and Women’s Sport Summit: Early Bird pricing ends 11 September

 Insight5 days ago
Women with birth trauma face 2.5x higher healthcare costs – study

 Menopause2 weeks ago
Cancer drug could tackle osteoporosis menopause weight gain

 News4 days ago
Medical cannabis may improve endometriosis symptoms – study

 Cancer5 days ago
Study could explain why obesity is a breast cancer risk factor

 Diagnosis2 weeks ago
FDA approves AstraZeneca breast cancer drug