



Interview: The race to close the gap on late-stage breast cancer diagnoses
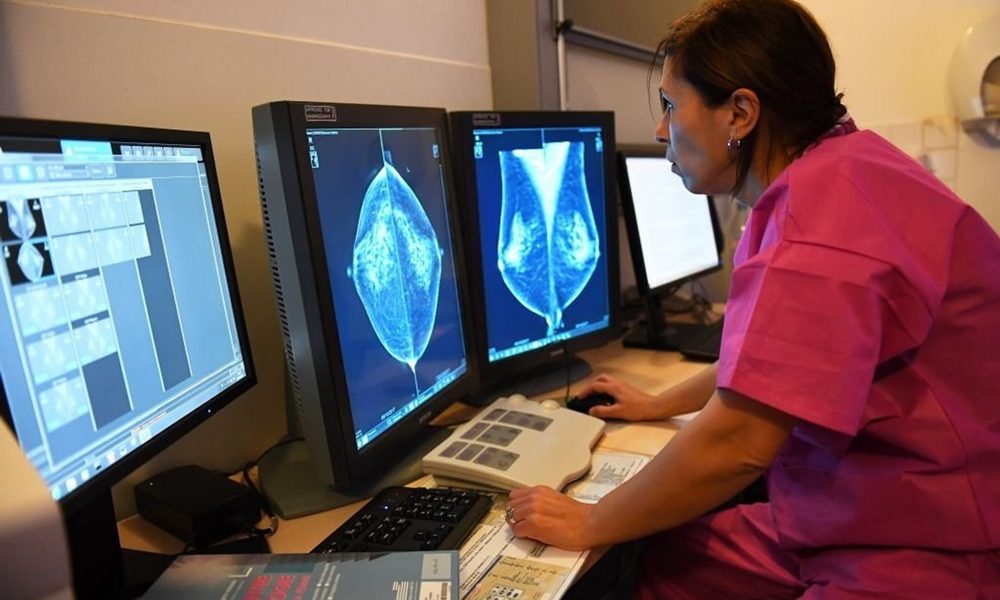
New research suggests that one in three eligible women in the US skip recommended mammograms – leading to late-stage breast cancer diagnosis, doubling treatment costs and increasing risk. Dr. Rani Aravamudhan, senior medical director at Nomi Health, speaks to Femtech World about addressing the problem, by helping employers and healthcare providers to reach women eligible for mammograms.
As part of its Trends in Spend series, Nomi Health has examined breast cancer screening and treatment data, finding that delayed detection negatively impacts patient outcomes and significantly increases financial burden.
Key findings from the report reveal that, while screening rates among women aged 40 to 74 have improved in recent years, over one-third continue to miss mammograms screenings at the recommended frequency, leaving significant gaps in preventive care.

Nomi highlights that unscreened women with advanced-stage breast cancer face treatment costs of up to US$120,485 which is US$44,029 more than screened patients at the same stage.
They are also more than twice as likely to be diagnosed with metastatic cancer.
Improving access and awareness
Currently, women over 40 are recommended to have a mammogram screening annually or bi-annually.
However, despite the year-over-year rate slowly trending upwards, still only around 63 per cent of eligible women are receiving their mammograms.
In order to improve screening uptake, Aravamudhan emphasises the importance of increasing awareness of mammograms.
“Despite the amount of data showing that mammograms are available at no out-of-pocket cost, not all women are aware of this – and I say that sympathetically- the healthcare system can be confusing,” says Aravamudhan.
“People wonder: what’s covered under my plan? I believe the system has become unnecessarily complex over the years, and that complexity discourages people from seeking care when they should.
“Certain services like annual physicals, mammograms, and colonoscopies must be made available to everyone at zero out-of-pocket cost.
“However, whether that’s true depends on someone’s insurance – often only if they go to an in-network facility. If they go out-of-network, they might still be charged. Understanding what’s in-network and what’s not can take real effort.”
Another barrier to mammogram uptake is access to these screenings, says Aravamudhan, highlighting that even in urban areas with ample facilities, getting an appointment isn’t always easy, with long wait times pushing back diagnoses.
“Even if financial access is fine, practical access is another issue. You need somewhere close by that can see you soon,” says Aravamudhan.
“In a rural or lower-income area, someone might need to travel 30 minutes or more just to reach a facility, they may have to take half a day off work for a 20-minute procedure.
“This is a very real, very practical problem. There are currently encouraging efforts though – some organisations, whether non-profits, hospital systems, or insurers have mobile units that go out to communities. These allow women to come to the unit, get their mammogram, and go.
“This is the kind of accessibility we need to expand.”
Aravamudhan suggests that these mobile units could also visit workplaces and retail stores to improve screening accessibility and reduce time needed off work for women.
“When we talk about access, it’s multi-layered,” says Aravamudhan.
“A relationship with a primary care provider (PCP) is also vital. Studies consistently show that when patients have a strong relationship with a PCP – someone who regularly checks in and encourages them to get screened – they are more likely to follow through.
“That trusted relationship leads to better compliance. And it’s not just mammograms – the same goes for Pap smears, colonoscopies, and so on.
“The provider doesn’t need to be forceful, just clear that this matters. It helps when they explain why it’s important and follow up. That relationship with a PCP matters a lot – not only for preventative screenings but for so many aspects of healthcare.”
Effective intervention for better outcomes
Awareness and access issues are contributing to delayed diagnosis, and Nomi’s analysis reveals that delayed diagnosis leads to an increase in the severity of treatment required.
Aravamudhan says employers, health plans, and healthcare providers all have a role to play in intervening more effectively to promote early detection.
“Employers are the ones providing health insurance for their employees and their dependents, so they have a significant stake in all of this,” says Aravamudhan.
“It’s crucial that we all – collectively – promote the value and benefits of preventive care early and often.
“It’s not just about getting a test or having a screening. It’s about investing in the health of our population. As individuals, we have a responsibility to do that for ourselves too. If I don’t invest in my own health, I risk having health issues that could impact my ability to work – and that, in turn, affects my family.
“Employers and health plans can do more during annual enrollment periods – not just talk about plan options, but also highlight the importance of preventive care with clear, relatable examples.
“They can share real stories – with permission – or public examples, such as someone well known who caught cancer early through screening and is now doing well. That kind of storytelling works and makes it real.
“Just like we reassure our children before a dentist visit, we need to normalise preventive care. It’s uncomfortable, but not painful – and it only takes 20 minutes. That kind of messaging – from colleagues, managers, health champions – can make a big difference.
“Reminders also help – as long as they’re targeted. Younger people may respond better to texts or emails, older people to phone calls. Tailor the channel to the audience.”
Another tool employers could utilise are incentives, says Aravamudhan, highlighting that many employers have healthcare rewards schemes
“Data shows that only a small percentage of people maximise those benefits,” says Aravamudhan.
“So there’s a lot of room for improvement – and a lot of opportunity to drive better engagement and health outcomes.”
Preventative care as a cost containment strategy
The Nomi analysis revealed that women who did not go for their mammograms who are diagnosed with advanced-stage breast cancer face treatment costs of up to $120,485, a total of $44,029 more than screened patients at the same stage.
The average cost per breast cancer episode was $25,765 for unscreened women, 18 per cent higher than for those who received their routine screenings.
In order to prevent these costs, Aravamudhan says that investment is needed in preventive care – whether employers, individuals or the wider system.
“I’m talking about continuous preventive care – a consistent, system-wide approach,” says Aravamudhan.
“It starts with disease prevention – such as vaccinations, for example. We absolutely should be promoting vaccines. We’ve already seen the consequences – falling vaccination rates in some areas like Texas have led to outbreaks of measles. Children are being hospitalised, some placed on ventilators, and tragically, some have died. That’s the real cost – not just financial, but lives lost.
“The next level of preventive care is screening. If someone is going to develop something like breast or cervical cancer, let’s catch it early.
“Early detection means a far better chance of survival and a much lower cost of treatment.
“Preventive care evolves into monitoring. We don’t just walk away after someone’s been treated for cancer – we continue to monitor them to make sure it doesn’t return, or to catch any new risks early. That’s still preventive care – just at a different stage.
“There is also chronic condition management. That might mean lifestyle changes, medication compliance, following a low-salt diet – whatever it takes. That kind of support system is key.
“And let’s not forget mental health. People often overlook preventive care in this space, but it absolutely exists. Building strong, consistent relationships with clinicians – whether through your GP, your insurer, or a nurse care manager – really matters.
“Those ongoing connections ensure preventive care stays front and centre. It helps reduce the long-term impact of conditions, and it lowers costs over time.
“All of this leads to healthier, happier families – and ultimately, far lower costs for employers. The alternative is simply more expensive – financially, socially, and emotionally.”

Newsletter
Sign up for free weekly updates
The latest femtech news, research and investment, straight to your inbox.



