




Opinion
Insight: Perimenopause, menopause and your mental health and wellbeing


By Dr Haleema Sheikh, a specialist in integrative women’s health and bioidentical hormone balancing for the Marion Gluck Clinic.
Perimenopause refers to the menopausal transition phase in women’s lives when the levels of reproductive hormones become more variable, and they can start to experience physical and mental symptoms related to these changes.
Menopause is diagnosed when a woman has not had a period for 12 consecutive months, and this usually happens between the ages of 45 and 55.
Hormones are our bodies chemical communication messengers which are carried in the blood stream around the body and are responsible for modulating and regulating activity in all our organs and tissues.
Women have receptors for the reproductive hormones produced in the ovary and adrenals (estrogen, progesterone and testosterone) in every tissue in the body including the brain. Thus, the hormonal imbalances during perimenopause and loss of hormones during menopause can have significant far-reaching consequences on our mental health.
Women are more susceptible to hormonal mental health issues as there is a complex interplay of reproductive hormones which need to be in sync to have a regular menstrual cycle.
This delicate interplay is often disrupted during perimenopause with estrogen not being balanced by progesterone (our soothing calming sleep supporting hormone) and then as we progress into menopause, we also lose the supportive effects of estrogen on the brain.
Women’s ovaries have a finite lifespan and during perimenopause which can start on average 6 years before menopause there can be significant hormonal disruption.
Women may start to have anovulatory cycles where they don’t ovulate each month and this results in estrogen being dominant as there is no progesterone rise in the second half of the cycle without ovulation. The lack of progesterone will also impact sleep quality and length which can further disrupt our mental health.
Progesterone enhances the activity of gamma-aminobutyric acid (GABA), a neurotransmitter that promotes relaxation and reduces anxiety. This is why low progesterone levels can contribute to increased stress, irritability, and anxiety which are often seen in perimenopause.
Progesterone is generally the first hormone to be lost in perimenopause. Unfortunately, many women are diagnosed with depression and anxiety at this time and are given antidepressants which may be helpful but do no tackle the root cause which is hormonal disruption.
Estrogen has powerful positive effects on the female brain, affecting mood, memory, cognition, and emotional well-being. It
plays a key role in neurotransmitter activity and boosts serotonin (the happiness hormone) and dopamine which help regulate mood and motivation. Estrogen also enhances the stress response; it modulates cortisol, the stress hormone, helping women cope with pressure more effectively.
By regulating sleep patterns through its influences on melatonin and circadian rhythms it also improves sleep quality and resilience which are key for mental health.
Coming onto Testosterone – it is not just a male hormone and it plays a crucial role in women’s brain health, energy levels and mood. Though women have lower testosterone levels than men, this hormone is essential for mental clarity, motivation, emotional resilience, and overall well-being.
Testosterone levels can be maintained by some women till later in menopause, but a significant proportion of women will have symptomatic loss of testosterone in perimenopause and so it is important to be aware of symptoms and test blood levels if considering support.
Testosterone has a mood stabilising effect and improves emotional wellbeing. It is also involved in neurotransmitter regulation and thereby reduces mood swings, stress and depressive symptoms. It also helps with enhanced confidence and motivation which gives women a sense of self assurance and emotional resilience in their lives.
The brain also receives feedback from the body and the gut and brain are deeply connected through the gut-brain nerve axis.
Changes in the gut microbiome (the friendly bacteria which reside in the large intestines) during menopause can significantly affect mood, mental health, and cognitive function.
As estrogen declines, the composition of the gut microbiome shifts, leading to inflammation, neurotransmitter imbalances, and increased stress response, which ultimately can contribute to anxiety, depression, and mood swings.
The gut communicates with the brain ‘telling’ it that the body is in a hostile environment and puts the brain into a high alert mode which can trigger hypervigilance and anxiety.
Ninety per cent of serotonin (the ‘happiness hormone’) is produced in the gut. Gut dysbiosis (an imbalance of good and bad bacteria) which is more common in menopause can disrupt serotonin and dopamine production, leading to depression, anxiety, and mood swings.
Low estrogen also leads to increased gut permeability (leaky gut), allowing inflammatory molecules and toxins to enter the bloodstream. This triggers neuroinflammation, which is linked to brain fog, fatigue, and low mood.
Healthy gut bacteria help regulate cortisol, the stress response hormone. An unbalanced microbiome can lead to higher cortisol levels, making women more prone to stress, panic, and emotional ups and downs.
The gut microbiome also influences melatonin (our sleep hormone). Dysbiosis can lead to insomnia, night wakings, and poor sleep quality, worsening irritability and emotional instability.
There are many signs and symptoms that may indicate the need to support hormonal balance which make sense now that we understand the impact of the hormones on the brain and body
• Frequent emotional ups and downs that disrupt daily life.
• Overwhelming anxiety or panic episodes.
• Difficulty focusing or remembering simple things.
• Persistent sadness or loss of joy.
• Chronic fatigue and lack of motivation.
• Feeling disconnected or unlike yourself.
• Irritability
• Low self-esteem and loss of confidence
There are many ways to restore balance, and a multipronged approach often works well:
• Lifestyle changes – Regular exercise, a healthy diet, and stress management are key to happy hormonal balance.
• Hormone therapy or Supplements – can be very helpful to help cushion the loss of ovarian function. Body identical and bioidentical hormones have the same molecular and chemical structure to our own hormones and have been shown to support the mental health issues that many women face
• Mental health support – Therapy, mindfulness, or journaling can be helpful to process the changes and build resilience.
• Sleep hygiene – Create a relaxing bedtime routine to improve rest is key to remaining high functioning and rebalance the system.
• Social support – Connecting with friends, support groups, or loved ones is protective for women going through this period.
Perimenopause and menopause often hit women during a time in their lives when they are juggling many balls including challenging careers, teenage children, spouse/partner, running a house and possibly looking after elderly parents.
The reproductive hormones provide resilience in the system which diminishes at this time. It is helpful for women to understand what is going on in their bodies during this transitional time and be kind to themselves as they recalibrate to lower hormone levels which can most certainly be done successfully.
The Marion Gluck Clinic is a UK-based medical clinic which uses bioidentical hormones to treat menopause, perimenopause and other hormone related issues.














A new clinical study has found that an at-home device for tracking reproductive hormones can identify ovulation with an accuracy that closely matches hospital-grade ultrasound scanning, in what researchers describe as a significant step for women’s health technology.
The findings, published this week in Reproductive BioMedicine Online, come from an 18-month trial led by Dr Thomas P. Bouchard that followed 121 ovulatory cycles and included 890 transvaginal ultrasound scans.
The study compared results from the Mira at-home hormone monitor, which tracks four hormones through urine samples, against the two methods long considered the clinical gold standard: ultrasound-confirmed ovulation and blood serum testing.
Researchers found that the day of ovulation, as confirmed by repeated ultrasound scans, fell within a day of the peak in luteinising hormone (LH) detected by the device in 96 per cent of cycles studied.
A new benchmark after 25 years
The study’s authors say it represents the first time a quantitative, multi-hormone at-home monitor has been validated against blinded ultrasound scanning under STARD guidelines, the internationally recognised standard for reporting diagnostic accuracy research.
Existing consumer fertility trackers, they note, have largely relied on simpler yes/no hormone readings or date-based algorithms that have gone unchanged for a quarter of a century.
The device tracks four hormones: LH, the oestrogen metabolite E13G, the progesterone metabolite PDG, and follicle-stimulating hormone (FSH).
What the data showed
Alongside the headline ultrasound comparison, researchers reported several other findings:
- Blood test correlation: readings from first-morning urine samples closely tracked blood serum levels drawn within 90 minutes, with the strongest correlation for LH, followed by progesterone and oestrogen metabolites, and a weaker but still notable link for FSH.
- Hidden variability in “regular” cycles: even among participants with typically regular periods, 11 per cent of cycles were found to be anovulatory, meaning no egg was released. In a further 12.4 per cent of cycles, ovulation occurred while LH was still climbing rather than after it peaked – a pattern researchers say calendar-based apps and single-day tests would likely miss.
- Earlier warning of fertility window: rising oestrogen signals were detectable roughly five to six days before ovulation, reflecting the natural development of ovarian follicles and offering an earlier indication of the fertile window than LH tracking alone.
‘Precise biological data without the clinic visits’
Dr Bouchard, the study’s lead author, said the research set a new bar for evaluating consumer fertility devices.
“For over two decades, at-home fertility tracking was based on qualitative indicators without providing quantitative hormone values,” he said, adding that testing the device against nearly 900 ultrasound scans under a blinded protocol gave the field a rigorous new benchmark.
Sylvia Kang, founder and chief executive of Mira, said the results pointed to a broader shift in how reproductive health could be monitored.
“Women deserve precise biological data about their reproductive health without needing constant clinic visits and serial blood draws,” she said, describing the findings as evidence that at-home testing could deliver “clinic-grade hormonal visibility.”

Sahar Abid is a Science Associate at Ema EQ, where she works on cultural sensitivity and bias in AI.
A woman asks an AI health assistant about postpartum depression.
She mentions that her in-laws are telling her to “push through” and skip medical help, even as her symptoms get harder to manage. She never says where she is from or names her background.
The assistant describes the condition and gives her a hotline number. It sounds correct, but it misses what she needs.
That gap is more common than the industry admits, and it points to a blind spot in how we test health AI for bias.
Most bias testing looks at what people explicitly say.
The typical way to check an AI for bias is to label a prompt with someone’s demographic details and see if the answer changes. That catches some problems but misses a bigger one.
Most people do not lead with their identity. They lead with their situation. The woman above told the assistant everything it needed to help her, just not in the form of a label.
Her real question was not only “what is postpartum depression?” It was “how do I get care when the people around me don’t want me to?
When family members hold sway over health decisions, and in many communities they do, advice that asks someone to overrule their family is not something they can act on.
The AI didn’t say anything factually wrong. It answered a different question than the one she was living.
We call this culturally implicit bias, meaning the AI misses the cultural context a situation implies rather than the context a person spells out.
When systems are trained to notice only the explicit cues, they fall back on a default answer built for the majority. For everyone else, the response can feel generic, off-target, or discouraging enough that they stop looking for help.
In health, that is not small. The people most likely to be missed are often the ones the system already underserves.
What we set out to test.
At Ema, we wanted to know how well AI picks up on cultural context that is implied but never stated. So we built our own way to test for it, across a range of communities and real situations like postpartum depression and fertility, using questions that carried cultural meaning without announcing it.
The patterns were consistent. Models often missed the meaning underneath the question. They dropped the specific details a person did share and smoothed them into something generic.
And even when they pointed toward real care, they tended to offer one option instead of choices that might actually fit a person’s life. Any one of those can be the difference between someone following the advice and walking away from care.
Why this matters for anyone building health AI.
Getting this right is the right thing to do, and it also works better.
When an answer reflects a person’s real context, people trust and act on the recommendations more, so they get the help and support they need.
Testing for it is harder than the shortcut most teams use. Swapping a name or a demographic label in and out is easy. Checking whether a model actually understands the human context around a question takes more care.
The shortcut teaches models to perform cultural competence instead of practicing it. No matter how much or how little someone chooses to share, they deserve an answer that is warm, complete, and usable.
A better question.
The bar for equitable health AI should be “does it serve someone who never told you who they are?” It is the harder test, but it determines whether real people get help.
The work of getting there is far from finished, and it is exactly what we are building toward at Ema.
Sources: Naidoo, V., & Chadha, K. K. (2025), Culturally responsive AI chatbots: from framework to field evidence, Computers in Human Behavior: Artificial Humans. Souligne, N., & Subbian, V. (2026), FairLogue: A toolkit for intersectional fairness analysis in clinical machine learning models.


A perimenopause app that maps existing smartwatch data to the menopausal transition has launched across 39 markets in the UK and Europe.
anna app uses information already recorded by wearables, including sleep, heart rate and body temperature, and returns one suggested lifestyle action each morning alongside the research behind it.
The company says each rule in its library links a defined pattern in a woman’s own data to a specific action. The recommendations were developed with an advising clinician and draw on more than 300 published studies.
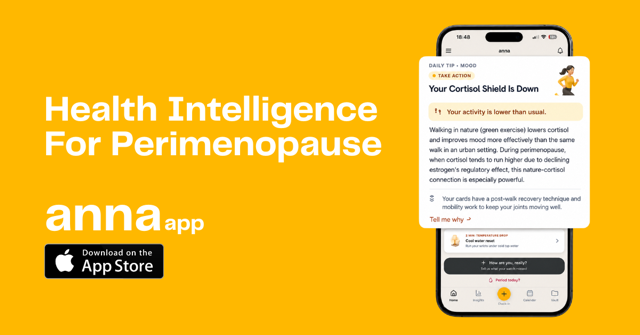
The company says recommendations are not generated automatically and each can be traced to research reviewed by a doctor.
The app was built by two women in Riga, has been funded without outside investment and was tested with women in the UK over three months before launch.
Perimenopause is the period of hormonal change before periods stop and usually begins after 40.
The company says one of the challenges is the unpredictability of the transition, with sleep, energy, mood and concentration potentially changing from week to week.
Because the experience varies between women, the developers say it can be difficult to find care tailored to individual needs. After 45, there is also no reliable blood test to confirm perimenopause.
The transition can coincide with a busy period in women’s working lives.
CIPD research published in 2023 found that 27 per cent of working women aged 40 to 60 with menopause symptoms said they had affected their career progression, equivalent to around 1.2m women in the UK.
Some 79 per cent said they felt less able to concentrate.
The long-running Study of Women’s Health Across the Nation, which has followed thousands of women through the menopausal transition, found that cognitive difficulties reported during perimenopause appear to be time-limited, with improvement returning in early postmenopause.
The developers say anna differs from standard wearable data by interpreting measurements specifically in the context of perimenopause.
A smartwatch may show changes in sleep, heart rate or temperature, but anna is designed to look at combinations of those signals and link them to lifestyle guidance for that day.
The app is also designed to work without daily symptom logging.
Users can complete an optional daily check-in if they want to add more context, but the app can operate without a symptom diary or daily manual entries.
It uses information from a compatible device the user already owns, such as a watch, ring or band.
Elina Pika-Lepere, co-founder and chief executive of anna app, said: “Perimenopause arrives exactly when a woman has the least spare capacity. She is often at the peak of her career, raising children, caring for ageing parents. What she has lost is not information, it is predictability.
“We built anna to offer a helping hand and evidence-based guidance through a stage that is difficult but temporary.”
The company gave the example of a morning when a user’s watch shows she has slept well below her own 28-day average.
Rather than simply telling her she is tired, anna may suggest choosing one priority and working on it in 25-minute blocks with a short break between them.
The app also displays the sleep and concentration research used for the recommendation.
anna was founded by Pika-Lepere, who spent 15 years building products in advertising, retail and e-commerce, and product lead Zanda Freimane, whose background is in product management in fintech and e-commerce.
The wider team includes a mathematician and university researcher advising on data architecture, a senior developer and a user experience adviser from a Baltic unicorn company.
anna app is not a medical device and does not provide medical advice.
Its guidance is limited to lifestyle support, and the company describes the app as a tool to complement a doctor rather than replace professional medical care.
anna app is available on iOS across 39 markets in the UK and Europe and is listed on the App Store as anna: Perimenopause & Sleep.
The app is in English and works with Apple Watch, Garmin, Fitbit, Oura and Whoop through Apple Health.
The company says user data is hosted in the EU and is never sold.
The service costs £13.99 a month or £99.99 a year in the UK and €14.99 a month or €99.99 a year in the euro area after a seven-day free trial.










 Menopause6 days ago
Menopause may not explain rising heart condition in women – study

 Pregnancy1 week ago
Paracetamol use may impact future fertility, studies suggest

 Events2 weeks ago
Last chance to save on Women’s Health Week and Women’s Sport Summit: Early Bird pricing ends 11 September

 Insight6 days ago
Women with birth trauma face 2.5x higher healthcare costs – study

 Menopause2 weeks ago
Cancer drug could tackle osteoporosis menopause weight gain

 News5 days ago
Medical cannabis may improve endometriosis symptoms – study

 Cancer6 days ago
Study could explain why obesity is a breast cancer risk factor

 Diagnosis2 weeks ago
FDA approves AstraZeneca breast cancer drug