




Diagnosis
False-positive mammogram results discourage women from future screenings


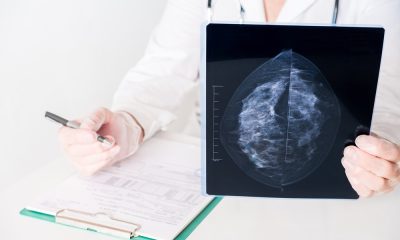
A new study has has found that women who received a false-positive result that required additional imaging or biopsy were less likely to return for that follow-up screening.
Early detection of breast cancer through mammography screening continues to save lives. However, abnormal findings on mammograms can lead to women being recalled for additional imaging and biopsies, many of which turn out to be “false positives,” meaning they do not result in a cancer diagnosis.
False positives can also have financial implications for patients and cause significant emotional anxiety.
The new study analysed data on more than 3.5 million screening mammograms nationwide performed between 2005-2017 on over 1 million patients aged 40 to 73.
“The finding raises concerns about the potential unintended consequence of false-positive results, where women may avoid screening mammograms in the future,” said lead author Diana Miglioretti, cancer center researcher and chief of the Division of Biostatistics at UC Davis.
Findings are worrisome to researchers
The study found that 77 per cent of women with a negative result from a mammogram returned for subsequent screening. But this percentage dropped to 61 per cent after a false-positive finding requiring another mammogram in six months to confirm the results and 67 per cent if a biopsy was recommended.
The impact was even more pronounced for women who received false-positive results on two consecutive mammograms recommending short-interval follow-up—only 56 per cent returned their next screening mammogram.
The high rate of women who don’t return for future screening is concerning to the research team.
“It is important for women with false-positive results to continue screening every one to two years,” Miglioretti said.
“Having a false-positive result, especially if it results in a diagnosis of benign breast disease, is associated with an increased risk of being diagnosed with breast cancer in the future.”
The research also showed that Asian and Hispanic/Latinx women were the least likely to return for future screening mammograms after a false positive result, which may contribute to existing health disparities.
False-positive results are common, especially among younger women. They occur in 10 to 12 per cent of mammograms in women 40 to 49 years of age. After 10 years of annual screenings, 50 to 60 per cent of women can expect at least one false-positive and 7 to 12 per cent at least one false-positive with a biopsy recommendation.
“It’s important to understand that most women recalled for additional imaging due to a finding on a screening mammogram do not have breast cancer,” Miglioretti said.
“They should try not to be worried if they are recalled for additional work-up. it is a normal and common part of the screening process.”
It is important for women to understand that about 10 per cent of the time, additional imaging is necessary to get a better look at a finding on a screening mammogram.
Steps to consider
Miglioretti said women who feel anxious while waiting for their screening mammography results might consider requesting an on-the-spot interpretation of their mammogram. Some facilities provide this service along with same-day diagnostic work-up, if there is a suspicious finding.
She said it is also important for physicians to carefully explain false-positive results to their patients to reassure them that the result was negative and stress the importance of continued screening.
The study was led by the UC Davis Comprehensive Cancer Center and published in the Annals of Internal Medicine.






Women with the same medical conditions as men were less likely to receive the same treatment across several specialties, a global research review found.
The review found differences in care for conditions including cardiovascular disease, kidney disease and Parkinson’s, with women less likely to receive some active treatments.
Of 38 studies analysed, 33 found women were less likely than men to be offered active treatment.

Researchers at the University of St Andrews found women with myocardial infarction, heart failure or an irregular heartbeat were more likely to receive medication, while men were more likely to undergo coronary bypass surgery, stenting or other surgical treatment.
Women were also less likely to be prescribed statins.
Men with Parkinson’s were more likely to be referred for deep brain stimulation.
Men with liver failure were more likely to receive a transplant, while women with kidney disease requiring dialysis were less likely to receive permanent access and spent longer using a catheter.
Women were also less likely to receive opioids for pain management.
The researchers found no significant difference between women and men in treatment for stroke or diabetes, while women were more likely to receive treatment for dementia.
None of the studies identified clinical guidelines recommending different treatment based on sex.
Researchers said this suggested the differences could not be explained by the need for different clinical approaches to women’s health.
Dr Andrew O’Malley, who co-led the study, said: “For clinicians, the findings are a prompt to check whether treatment is being offered on clinical grounds rather than assumption.”
He said studies showed doctors more often attributed women’s symptoms to anxiety and made more diagnostic errors with female patients, even when test results were positive.
Dr Miriam Veenhuizen, honorary lecturer in the School of Medicine at St Andrews, said: “While the direction of the findings was not a surprise, the consistency was. The same pattern appeared in cardiology, surgery, transplant medicine and emergency care, and it survived statistical adjustment in most studies.”


Menopause is often absent from women’s electronic health records, a study of nearly 396,000 women has found.
Researchers found menopause appeared almost seven times more often in participant surveys than in electronic health records (EHRs).
The findings suggest important reproductive health information, including age at menopause, may often be missing from health records used for research.
Audrey Hendricks, associate professor of bioinformatics at CU Anschutz and the study’s principal investigator, said: “Ultimately, we cannot study what we do not measure. We cannot treat what we do not know.
“Menopause has enormous implications for women’s health, but if we don’t consistently capture when menopause occurs and other important reproductive health information, we limit our ability to understand how this transition affects disease risk and health outcomes.”
Researchers at the University of Colorado Anschutz analysed data from women taking part in the National Institutes of Health’s All of Us Research Program.
They compared menopause information reported by participants in surveys with menopause diagnoses recorded in their electronic health records.
Around 193,000 menopause observations were identified in survey data, compared with approximately 28,000 diagnoses in EHR data.
Menopause was documented in electronic health records for only about 7 per cent of women in the dataset.
Nearly all participants with a menopause diagnosis recorded in their EHR also reported menopause in survey data. However, substantially fewer women had menopause documented in their health records.
Other important information was also frequently unavailable, including age at menopause, which researchers may use when examining links between menopause and chronic disease risk.
Menopause is a physiological transition that can affect cardiometabolic health and many other aspects of women’s health.
Researchers said relatively little is known about how factors including the timing and type of menopause influence health outcomes across diverse populations.
Large-scale programmes such as All of Us combine participant surveys, electronic health records and genomic data, but menopause-related research depends on relevant reproductive health information being available.
Missing menopause information can make it harder to investigate how the transition relates to health and disease.
The findings may also help researchers using All of Us data define menopause-related study populations, design studies and estimate how many participants are needed.
Hendricks said: “We have an enormous opportunity to use large-scale datasets to understand women’s health across the menopause transition and to identify who may be at greater risk for disease.
“But we need to make sure that the information researchers need is actually being collected.
“We must do a better job of capturing women’s health information, including reproductive health and measures related to menopause.”
Researchers said more complete and consistent collection of menopause and reproductive health information could help future studies examine factors such as age at menopause and their relationship with disease risk and health outcomes.









 Menopause1 week ago
Menopause may not explain rising heart condition in women – study

 Entrepreneur2 weeks ago
Last chance to save on Women’s Health Week and Women’s Sport Summit: Early Bird pricing ends 11 September

 Fertility2 weeks ago
Paracetamol use may impact future fertility, studies suggest

 Insight1 week ago
Women with birth trauma face 2.5x higher healthcare costs – study

 Cancer2 weeks ago
Cancer drug could tackle osteoporosis menopause weight gain

 News7 days ago
Medical cannabis may improve endometriosis symptoms – study
 Cancer1 week ago
Study could explain why obesity is a breast cancer risk factor

 Diagnosis2 weeks ago
FDA approves AstraZeneca breast cancer drug
2 Comments