




Opinion
Why clinical trials need more women – and how to make it happen


Clinical trials have enabled the healthcare industry to deliver to the world a plethora of innovative, life-saving medications from insulin to antibiotics to vaccines.
By Dr. Anita Phung, medical monitor for Lindus Health
However, one area where clinical trials have fallen notably short is women’s health. Women are notoriously underrepresented in clinical trials and research, creating gaps in our understanding of conditions critical to their wellbeing.
These gaps in women’s health research extend not only to key life stages marked by hormonal and physiological changes, such as menstruation, pregnancy and menopause, but also to cardiovascular, autoimmune and neurodevelopmental conditions. Historically, clinical research has centred on the male body as the default, leading to treatments and medical guidelines that may not fully account for female-specific biological and hormonal differences.
However, this has begun to change as new advances in the clinical trial industry help enable access to participation for women. From decentralised models to novel digital tools, new ways to improve women’s engagement in clinical trials are emerging.
How we got here
The exclusion of women from clinical trials has deep historical roots. Early clinical research primarily relied on male participants, often selecting participants from the military or prison populations. This male-centric approach was later reinforced by the thalidomide crisis in the 1960s, which led to regulatory measures barring women of childbearing potential from participating in clinical trials to protect potential pregnancies. While well-intentioned, these restrictions contributed to decades of missing data on how medical treatments affect women.

Even after progress in the late 1990s, when policies were introduced to increase women’s participation in clinical trials, significant disparities remain. A major issue is the continued exclusion of pregnant women, despite the fact that many require medical interventions during pregnancy. A recent study found that fewer than 1% of U.S. clinical trials enroll pregnant participants, leaving clinicians with limited guidance on how to safely prescribe medications for this population.
Beyond pregnancy, women undergoing menopause or experiencing menstrual cycle variations are also underrepresented in research. Hormonal fluctuations can influence how drugs are metabolized, yet these differences are often not considered in study designs. Additionally, metabolic conditions that disproportionately impact women, such as endometriosis and autoimmune disorders, are understudied.
Closing the gender gap
To bridge this gap, the clinical trial industry must adopt proactive strategies to increase women’s participation.
Here are four key solutions:
- Ensure greater representation of women in science: Increasing the number of women in leadership positions within research institutions and regulatory agencies can help prioritise female-focused research and encourage gender-sensitive study designs. More diversity in leadership leads to research questions that better reflect the healthcare needs of women, ensuring medical advancements are inclusive and relevant.
- Adopt digital tools: Wearable technology and FemTech solutions can help track hormonal cycles and improve data collection by capturing real-time health metrics that better represent women’s physiological fluctuations. Cardiovascular metrics, including heart rate, heart rate variability and arrhythmias, provide valuable insights, empowering women to seek timely medical attention, thereby reducing delayed presentations.
- Embrace decentralised clinical trial models: Many women, particularly caregivers or those in underserved communities, struggle to participate in traditional clinical trials due to logistical barriers. Decentralized trials, which allow remote participation through virtual visits and at-home data collection, can make research more accessible. These models also help to recruit a more diverse participant pool, ultimately leading to findings that are more representative of the broader population.
- Explore regulatory and incentive-based changes: Implementing policies that mandate gender-specific analyses in research and providing incentives for trials focused on women’s health can drive meaningful improvements. Regulatory bodies can further encourage compliance by integrating financial and ethical incentives for researchers to prioritize gender equity in study designs.
Conclusion
Addressing the underrepresentation of women in clinical trials is not just about equity — it is a matter of patient safety and clinical efficacy. Without robust data on how treatments affect women, medicine remains incomplete leaving healthcare providers left to make assumptions that can lead to suboptimal care. By integrating digital tools, embracing decentralized trial models, increasing female representation in science and ensuring regulatory frameworks prioritise women’s health, the industry can dismantle the barriers that have historically sidelined women in research.
As the healthcare landscape evolves, clinical research must advance alongside it. With intentional effort, we can create a future where medical advancements serve all individuals equitably, ensuring that women are not an afterthought but a priority and receive the same level of consideration and care in medical research as men.

As a Medical Monitor for Lindus Health, Dr. Anita Phung provides clinical oversight for research studies, drawing on her experience as a Portfolio GP with expertise in metabolic health, precision medicine and digital health.











A new clinical study has found that an at-home device for tracking reproductive hormones can identify ovulation with an accuracy that closely matches hospital-grade ultrasound scanning, in what researchers describe as a significant step for women’s health technology.
The findings, published this week in Reproductive BioMedicine Online, come from an 18-month trial led by Dr Thomas P. Bouchard that followed 121 ovulatory cycles and included 890 transvaginal ultrasound scans.
The study compared results from the Mira at-home hormone monitor, which tracks four hormones through urine samples, against the two methods long considered the clinical gold standard: ultrasound-confirmed ovulation and blood serum testing.
Researchers found that the day of ovulation, as confirmed by repeated ultrasound scans, fell within a day of the peak in luteinising hormone (LH) detected by the device in 96 per cent of cycles studied.
A new benchmark after 25 years
The study’s authors say it represents the first time a quantitative, multi-hormone at-home monitor has been validated against blinded ultrasound scanning under STARD guidelines, the internationally recognised standard for reporting diagnostic accuracy research.
Existing consumer fertility trackers, they note, have largely relied on simpler yes/no hormone readings or date-based algorithms that have gone unchanged for a quarter of a century.
The device tracks four hormones: LH, the oestrogen metabolite E13G, the progesterone metabolite PDG, and follicle-stimulating hormone (FSH).
What the data showed
Alongside the headline ultrasound comparison, researchers reported several other findings:
- Blood test correlation: readings from first-morning urine samples closely tracked blood serum levels drawn within 90 minutes, with the strongest correlation for LH, followed by progesterone and oestrogen metabolites, and a weaker but still notable link for FSH.
- Hidden variability in “regular” cycles: even among participants with typically regular periods, 11 per cent of cycles were found to be anovulatory, meaning no egg was released. In a further 12.4 per cent of cycles, ovulation occurred while LH was still climbing rather than after it peaked – a pattern researchers say calendar-based apps and single-day tests would likely miss.
- Earlier warning of fertility window: rising oestrogen signals were detectable roughly five to six days before ovulation, reflecting the natural development of ovarian follicles and offering an earlier indication of the fertile window than LH tracking alone.
‘Precise biological data without the clinic visits’
Dr Bouchard, the study’s lead author, said the research set a new bar for evaluating consumer fertility devices.
“For over two decades, at-home fertility tracking was based on qualitative indicators without providing quantitative hormone values,” he said, adding that testing the device against nearly 900 ultrasound scans under a blinded protocol gave the field a rigorous new benchmark.
Sylvia Kang, founder and chief executive of Mira, said the results pointed to a broader shift in how reproductive health could be monitored.
“Women deserve precise biological data about their reproductive health without needing constant clinic visits and serial blood draws,” she said, describing the findings as evidence that at-home testing could deliver “clinic-grade hormonal visibility.”

Sahar Abid is a Science Associate at Ema EQ, where she works on cultural sensitivity and bias in AI.
A woman asks an AI health assistant about postpartum depression.
She mentions that her in-laws are telling her to “push through” and skip medical help, even as her symptoms get harder to manage. She never says where she is from or names her background.
The assistant describes the condition and gives her a hotline number. It sounds correct, but it misses what she needs.
That gap is more common than the industry admits, and it points to a blind spot in how we test health AI for bias.
Most bias testing looks at what people explicitly say.
The typical way to check an AI for bias is to label a prompt with someone’s demographic details and see if the answer changes. That catches some problems but misses a bigger one.
Most people do not lead with their identity. They lead with their situation. The woman above told the assistant everything it needed to help her, just not in the form of a label.
Her real question was not only “what is postpartum depression?” It was “how do I get care when the people around me don’t want me to?
When family members hold sway over health decisions, and in many communities they do, advice that asks someone to overrule their family is not something they can act on.
The AI didn’t say anything factually wrong. It answered a different question than the one she was living.
We call this culturally implicit bias, meaning the AI misses the cultural context a situation implies rather than the context a person spells out.
When systems are trained to notice only the explicit cues, they fall back on a default answer built for the majority. For everyone else, the response can feel generic, off-target, or discouraging enough that they stop looking for help.
In health, that is not small. The people most likely to be missed are often the ones the system already underserves.
What we set out to test.
At Ema, we wanted to know how well AI picks up on cultural context that is implied but never stated. So we built our own way to test for it, across a range of communities and real situations like postpartum depression and fertility, using questions that carried cultural meaning without announcing it.
The patterns were consistent. Models often missed the meaning underneath the question. They dropped the specific details a person did share and smoothed them into something generic.
And even when they pointed toward real care, they tended to offer one option instead of choices that might actually fit a person’s life. Any one of those can be the difference between someone following the advice and walking away from care.
Why this matters for anyone building health AI.
Getting this right is the right thing to do, and it also works better.
When an answer reflects a person’s real context, people trust and act on the recommendations more, so they get the help and support they need.
Testing for it is harder than the shortcut most teams use. Swapping a name or a demographic label in and out is easy. Checking whether a model actually understands the human context around a question takes more care.
The shortcut teaches models to perform cultural competence instead of practicing it. No matter how much or how little someone chooses to share, they deserve an answer that is warm, complete, and usable.
A better question.
The bar for equitable health AI should be “does it serve someone who never told you who they are?” It is the harder test, but it determines whether real people get help.
The work of getting there is far from finished, and it is exactly what we are building toward at Ema.
Sources: Naidoo, V., & Chadha, K. K. (2025), Culturally responsive AI chatbots: from framework to field evidence, Computers in Human Behavior: Artificial Humans. Souligne, N., & Subbian, V. (2026), FairLogue: A toolkit for intersectional fairness analysis in clinical machine learning models.


A perimenopause app that maps existing smartwatch data to the menopausal transition has launched across 39 markets in the UK and Europe.
anna app uses information already recorded by wearables, including sleep, heart rate and body temperature, and returns one suggested lifestyle action each morning alongside the research behind it.
The company says each rule in its library links a defined pattern in a woman’s own data to a specific action. The recommendations were developed with an advising clinician and draw on more than 300 published studies.
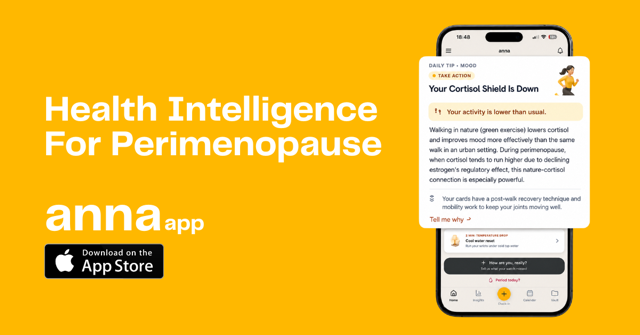
The company says recommendations are not generated automatically and each can be traced to research reviewed by a doctor.
The app was built by two women in Riga, has been funded without outside investment and was tested with women in the UK over three months before launch.
Perimenopause is the period of hormonal change before periods stop and usually begins after 40.
The company says one of the challenges is the unpredictability of the transition, with sleep, energy, mood and concentration potentially changing from week to week.
Because the experience varies between women, the developers say it can be difficult to find care tailored to individual needs. After 45, there is also no reliable blood test to confirm perimenopause.
The transition can coincide with a busy period in women’s working lives.
CIPD research published in 2023 found that 27 per cent of working women aged 40 to 60 with menopause symptoms said they had affected their career progression, equivalent to around 1.2m women in the UK.
Some 79 per cent said they felt less able to concentrate.
The long-running Study of Women’s Health Across the Nation, which has followed thousands of women through the menopausal transition, found that cognitive difficulties reported during perimenopause appear to be time-limited, with improvement returning in early postmenopause.
The developers say anna differs from standard wearable data by interpreting measurements specifically in the context of perimenopause.
A smartwatch may show changes in sleep, heart rate or temperature, but anna is designed to look at combinations of those signals and link them to lifestyle guidance for that day.
The app is also designed to work without daily symptom logging.
Users can complete an optional daily check-in if they want to add more context, but the app can operate without a symptom diary or daily manual entries.
It uses information from a compatible device the user already owns, such as a watch, ring or band.
Elina Pika-Lepere, co-founder and chief executive of anna app, said: “Perimenopause arrives exactly when a woman has the least spare capacity. She is often at the peak of her career, raising children, caring for ageing parents. What she has lost is not information, it is predictability.
“We built anna to offer a helping hand and evidence-based guidance through a stage that is difficult but temporary.”
The company gave the example of a morning when a user’s watch shows she has slept well below her own 28-day average.
Rather than simply telling her she is tired, anna may suggest choosing one priority and working on it in 25-minute blocks with a short break between them.
The app also displays the sleep and concentration research used for the recommendation.
anna was founded by Pika-Lepere, who spent 15 years building products in advertising, retail and e-commerce, and product lead Zanda Freimane, whose background is in product management in fintech and e-commerce.
The wider team includes a mathematician and university researcher advising on data architecture, a senior developer and a user experience adviser from a Baltic unicorn company.
anna app is not a medical device and does not provide medical advice.
Its guidance is limited to lifestyle support, and the company describes the app as a tool to complement a doctor rather than replace professional medical care.
anna app is available on iOS across 39 markets in the UK and Europe and is listed on the App Store as anna: Perimenopause & Sleep.
The app is in English and works with Apple Watch, Garmin, Fitbit, Oura and Whoop through Apple Health.
The company says user data is hosted in the EU and is never sold.
The service costs £13.99 a month or £99.99 a year in the UK and €14.99 a month or €99.99 a year in the euro area after a seven-day free trial.










 Menopause6 days ago
Menopause may not explain rising heart condition in women – study

 Fertility1 week ago
Paracetamol use may impact future fertility, studies suggest

 Entrepreneur2 weeks ago
Last chance to save on Women’s Health Week and Women’s Sport Summit: Early Bird pricing ends 11 September

 Insight6 days ago
Women with birth trauma face 2.5x higher healthcare costs – study

 Menopause2 weeks ago
Cancer drug could tackle osteoporosis menopause weight gain

 News5 days ago
Medical cannabis may improve endometriosis symptoms – study

 Cancer6 days ago
Study could explain why obesity is a breast cancer risk factor

 Diagnosis2 weeks ago
FDA approves AstraZeneca breast cancer drug