




News
Maven plans fresh investment into fertility and virtual care platforms


The world’s largest virtual clinic for women’s and family health has raised US$125m to further develop its fertility benefits and virtual care platforms.
This brings Maven Clinic’s total funding to more than US$425m, with this latest round coming from existing investors General Catalyst, Sequoia, Oak HC/FT, Icon Ventures, Dragoneer Investment Group, and Lux Capital.
More than 2,000 employers and health plans globally utilise Maven’s digital programmes, which provide clinical, emotional, and financial support to employees. Focus areas span fertility, maternity, parenting, paediatrics and menopause. Clients include Amazon, Microsoft, AT&T, Morgan Stanley and L’Oreal.
Maven will use the funds to further invest in Maven Managed Benefit, its fertility benefits administration platform. It will also support the further development of its virtual care platform.
Kate Ryder, founder and CEO, said: “Over the last 10 years, Maven has created and scaled a comprehensive virtual care model in one of the most underfunded sectors in healthcare
“The next decade is about transformation. We now have the platform breadth, depth, and data required to create the scaled change this industry so sorely needs. With each member supported, we continue to prove that to build better healthcare for everyone we must first build it for women and families.”
Maven Managed Benefit provides fertility education and “trying-to-conceive” coaching, giving couples a pathway to conceive without IVF, while also ensuring those who need IVF receive the support and benefits they need to reach a healthy pregnancy.
It has a network of 475+ fertility clinics which are integrated with virtual services, allowing members to get real time updates on their benefits and costs on the same platform they receive fertility education and coaching.
In the last year, Maven has become the largest fertility benefits provider globally by lives under management. Ryder founded the company in 2014.







Obesity may reduce a fat-cell process that helps kill breast cancer cells, offering a possible explanation for its link to the disease, a study found.
The findings come from preclinical models, including breast tissue from donors.

The research team at Huntsman Cancer Institute at the University of Utah focused on adipocytes, the fat cells that make up much of breast tissue.
Adipocytes are larger in obesity than in lean tissue and create different environments around cancer cells.
Researchers found that lean adipocytes produced much more of a fatty acid called 9S-HODE than obese adipocytes.
9S-HODE promotes ferroptosis, a form of cell death that helps the body remove old and damaged cells, including cells that could be cancerous.
Cancerous cells died more readily in lean tissue, where levels of 9S-HODE were higher.
Meghan Curtin, first author and a doctoral candidate in molecular biology, said: “We found that the lean adipocytes produce much more 9S-HODE than obese ones. This means that cancerous cells die more readily in lean tissue.
“By producing more 9S-HODE, our bodies are actively protecting us, under lean circumstances, in a way it cannot with obesity.”
In preclinical mouse models, increasing levels of 9S-HODE in obese adipocytes suppressed breast cancer tumour growth.
The researchers believe this understanding could lead to better therapies.
Keren Hilgendorf, senior author of the study and an investigator at Huntsman Cancer Institute, said: “From a clinical perspective, this discovery is incredibly empowering. Because 9S-HODE is naturally present in the body but is lost with obesity, we may be able to restore this protection by putting it back.”
“That could become a very feasible therapeutic approach to slow breast cancer growth.
The researchers stressed that obesity is only one factor that contributes to breast cancer and that the disease can develop for other reasons.
They also said 9S-HODE appears to be produced mainly by fat cells in the breast, although fat cells elsewhere in the body may have a similar protective function that requires further research.


Menopause may not drive rising pulse pressure after midlife, with changes beginning up to two decades before the final menstrual period, a study found.
Pulse pressure, the gap between the upper and lower numbers in a blood pressure reading, is influenced by the stiffness and width of the aorta, the body’s largest blood vessel.
The analysis found that women’s pulse pressure reached its lowest point and began rising in their late 30s, around a decade earlier than in men, regardless of when menopause occurred.
Researchers analysed data from the Framingham Heart Study, a long-running study of cardiovascular risk factors involving three generations of families in Massachusetts.
The study included 6,760 adult women assessed at three health visits over 14 years. Women were grouped according to whether they were premenopausal or experienced early, average or late menopause.
Women whose menopause was induced by surgery or medication were excluded. Researchers also analysed data from 3,248 adult men to examine differences between the sexes.
Pulse pressure typically falls between early adulthood and midlife as the internal space within the aorta increases in diameter, allowing blood to flow more easily.
After midlife, pulse pressure tends to rise as the aorta stops widening and its walls become stiffer. A wider pulse pressure means the heart has to work harder and can contribute to damage in small blood vessels in organs including the brain and kidneys.
The researchers found that the age at which women’s pulse pressure changed from falling to rising was not affected by whether their final menstrual period occurred early, late or at a typical age.
After midlife, pulse pressure increased with age in both women and men, although it rose faster among women. Average pulse pressure was higher in women than men after the age of 60.
Gary F. Mitchell, senior author of the study, said: “To our huge surprise, our results suggest that factors other than the timing of the final menstrual period were likely involved in the accelerated increase in pulse pressure in women after midlife.”
The findings challenge the assumption that hormonal changes associated with menopause contribute to the increase in aortic stiffness seen among women later in life.
However, the observational study could not establish cause and effect. It also relied on participants reporting their age at menopause rather than researchers measuring oestrogen levels.
Most participants were of white European descent, meaning the findings may not apply to people from other racial or ethnic groups.
Wide pulse pressure is an independent risk factor for cardiovascular disease, dementia and kidney disease, according to the researchers, although pulse pressure is not currently included in clinical guidelines for managing blood pressure.
Mitchell said healthcare professionals should consider pulse pressure when assessing middle-aged and older people with high blood pressure, particularly women.
Samar R. El Khoudary, who was not involved in the study, said the findings did not mean menopause had no role in women’s cardiovascular health.
“Vascular aging may begin years before menopause, but that doesn’t mean menopause is irrelevant. The trajectory may accelerate as women enter perimenopause.
“We shouldn’t wait until menopause to start thinking about cardiovascular health.
“By the time a woman reaches her final menstrual period, vascular changes may already have been underway for years. Midlife is an opportunity to identify cardiovascular risk early and intervene before disease develops.”
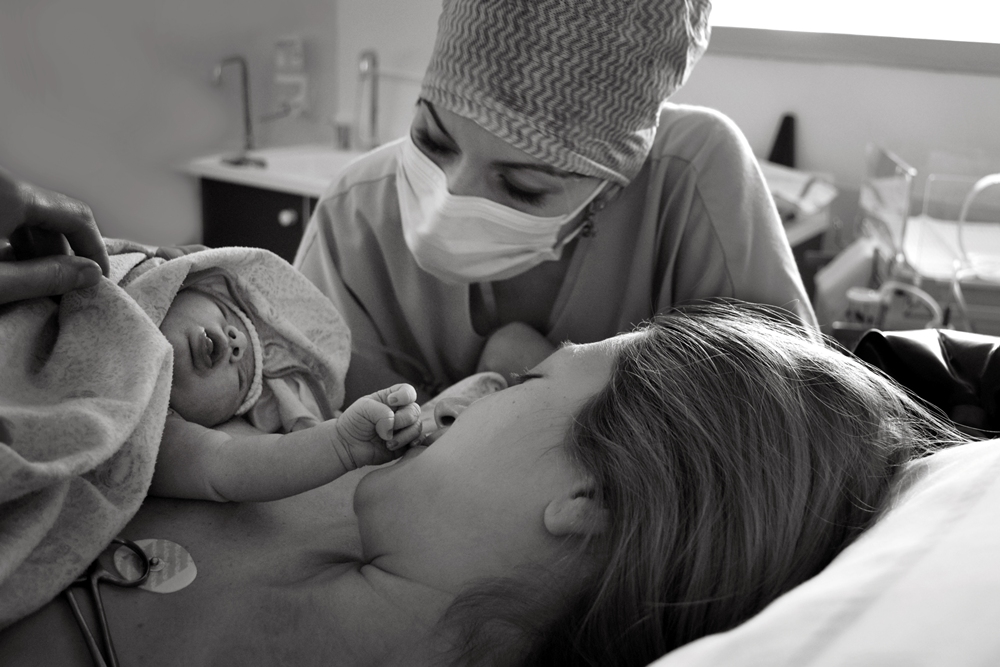
Women with childbirth-related PTSD had healthcare costs 2.5 times higher than women without PTSD from six to 12 months after birth, a report found.
The analysis estimated that early prevention of traumatic births and childbirth-related post-traumatic stress disorder (PTSD) could save the NHS around £26m each year.
Women with PTSD were also less likely to have returned to work by 12 months after giving birth, suggesting potential longer-term employment and economic effects.
The report from City St George’s, University of London was launched at an All-Party Parliamentary Group (APPG) on Birth Trauma event on 10 September 2026.
Researchers calculated the potential NHS savings using the number of births reported in NHS hospitals in 2024-25 and the UK prevalence of childbirth-related PTSD.
Around one in 20 women in the UK develop PTSD following childbirth, while recent research has shown that the condition remains underdiagnosed.
The findings draw on research that tracked more than 2,000 women in England and Scotland from pregnancy to two years after birth. Researchers assessed mental health, use of health services and employment outcomes.
The research included assessments of childbirth-related PTSD and PTSD arising from other traumatic experiences. It also included a separate Birth Trauma Association survey examining women’s experiences of birth trauma.
Between six and 12 months after birth, healthcare and support service costs for women with childbirth-related PTSD were 2.5 times those of women without PTSD.
Women with low or moderate symptoms, including those reporting one or two PTSD symptoms, also had higher healthcare service costs than women without PTSD.
Just over half, 53 per cent, of women with PTSD had returned to work by 12 months after giving birth, compared with 68 per cent of women without symptoms.
Women with PTSD were more likely to be referred for mental health support, but more than half received no referral.
Those whose PTSD followed a traumatic birth also had slightly higher healthcare costs than women whose PTSD resulted from other traumatic experiences.
The researchers called for routine PTSD assessment and treatment during pregnancy and after childbirth, alongside greater access to specialist perinatal mental health services.
They also recommended training healthcare staff in perinatal trauma, trauma-informed care and identifying women at risk of PTSD.
The report said further research was needed to establish whether screening, treatments and trauma-informed care pathways are effective and evidence based.
The work follows the APPG’s 2024 Birth Trauma Inquiry, which highlighted the effects of birth trauma on women and families and called for evidence on its wider public health and societal costs.
The report focused primarily on healthcare use and did not attempt to calculate all costs associated with birth trauma and postnatal PTSD, including wider employment, family and societal effects.










 Pregnancy2 weeks ago
KOVE Medical raises €1.7 million to improve safety of foetal surgery

 Pregnancy2 weeks ago
UK study aims to transform maternity care for high-risk pregnancies

 Pregnancy5 days ago
Paracetamol use may impact future fertility, studies suggest

 Entrepreneur1 week ago
Last chance to save on Women’s Health Week and Women’s Sport Summit: Early Bird pricing ends 11 September

 Menopause2 weeks ago
Menopause hormone treatment may ease brain fog, study suggests

 Menopause7 days ago
Cancer drug could tackle osteoporosis menopause weight gain

 News2 weeks ago
Spanish agency criticised for menopause guidelines based on male studies

 Fertility2 weeks ago
NHS IVF access review launched in Scotland
3 Comments