




Insight
Early PET scan could chemo response in aggressive breast cancer – study
















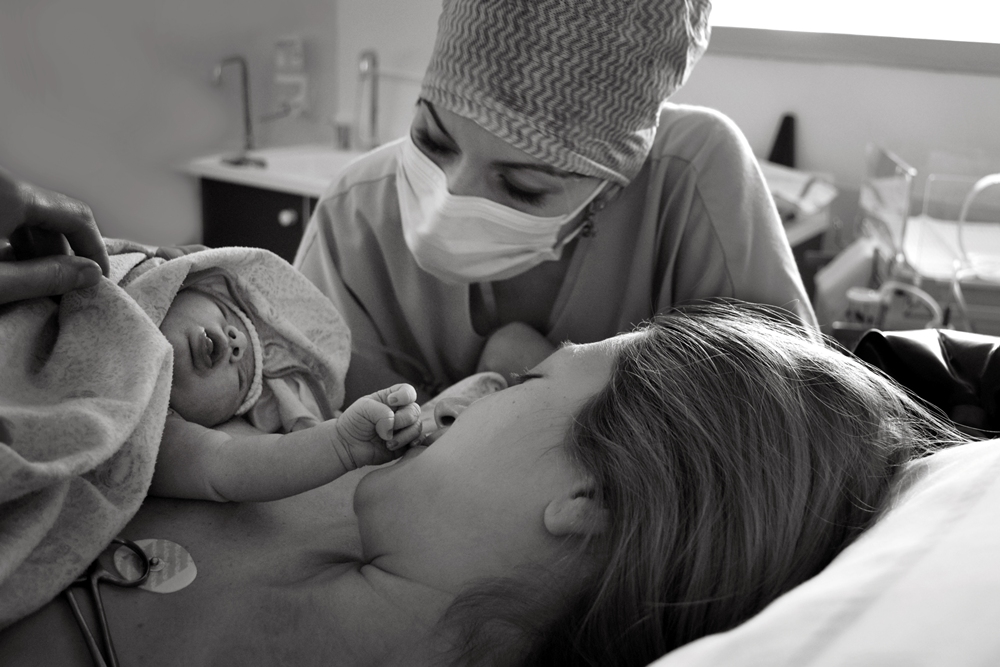
Women with childbirth-related PTSD had healthcare costs 2.5 times higher than women without PTSD from six to 12 months after birth, a report found.
The analysis estimated that early prevention of traumatic births and childbirth-related post-traumatic stress disorder (PTSD) could save the NHS around £26m each year.
Women with PTSD were also less likely to have returned to work by 12 months after giving birth, suggesting potential longer-term employment and economic effects.

The report from City St George’s, University of London was launched at an All-Party Parliamentary Group (APPG) on Birth Trauma event on 10 September 2026.
Researchers calculated the potential NHS savings using the number of births reported in NHS hospitals in 2024-25 and the UK prevalence of childbirth-related PTSD.
Around one in 20 women in the UK develop PTSD following childbirth, while recent research has shown that the condition remains underdiagnosed.
The findings draw on research that tracked more than 2,000 women in England and Scotland from pregnancy to two years after birth. Researchers assessed mental health, use of health services and employment outcomes.
The research included assessments of childbirth-related PTSD and PTSD arising from other traumatic experiences. It also included a separate Birth Trauma Association survey examining women’s experiences of birth trauma.
Between six and 12 months after birth, healthcare and support service costs for women with childbirth-related PTSD were 2.5 times those of women without PTSD.
Women with low or moderate symptoms, including those reporting one or two PTSD symptoms, also had higher healthcare service costs than women without PTSD.
Just over half, 53 per cent, of women with PTSD had returned to work by 12 months after giving birth, compared with 68 per cent of women without symptoms.
Women with PTSD were more likely to be referred for mental health support, but more than half received no referral.
Those whose PTSD followed a traumatic birth also had slightly higher healthcare costs than women whose PTSD resulted from other traumatic experiences.
The researchers called for routine PTSD assessment and treatment during pregnancy and after childbirth, alongside greater access to specialist perinatal mental health services.
They also recommended training healthcare staff in perinatal trauma, trauma-informed care and identifying women at risk of PTSD.
The report said further research was needed to establish whether screening, treatments and trauma-informed care pathways are effective and evidence based.
The work follows the APPG’s 2024 Birth Trauma Inquiry, which highlighted the effects of birth trauma on women and families and called for evidence on its wider public health and societal costs.
The report focused primarily on healthcare use and did not attempt to calculate all costs associated with birth trauma and postnatal PTSD, including wider employment, family and societal effects.


The UK government is reviewing a surrogacy firm after complaints that medical insurance claims involving surrogates in Mexico were rejected.
The Department of Health and Social Care (DHSC) is considering whether UK-based provider My Surrogacy Journey should remain listed on gov.uk as one of four domestic surrogacy agencies available to intended parents.
The review follows allegations concerning its Mexican sister company, where surrogates are based.
Health minister Diana Johnson said: “The department is looking into the allegations about My Surrogacy Journey.
“As part of that assessment, the department will consider whether it is appropriate for that company to remain on the gov.uk list of agencies.”
Emails sent by My Surrogacy Journey chief executive Michael Johnson-Ellis and seen by the Guardian suggest multiple surrogate women in Mexico had their insurance claims rejected.
The emails also suggest 300 couples using the company were moved to a new insurance provider because of the increased risk of claims being rejected.
Commercial surrogacy is banned in the UK, where only altruistic arrangements are permitted.
My Surrogacy Journey operates a not-for-profit UK branch alongside for-profit sister companies in Mexico and the US. All three companies have the same owners and chief executives.
The reported insurance issues relate to surrogacy arrangements in Mexico.
One couple told the Guardian they paid tens of thousands of pounds to cover medical costs after their surrogate had a hysterectomy during childbirth and an insurance claim was refused.
The Guardian said it understood that at least five sets of parents said they had to cover medical costs after insurance claims were rejected.
In an email to the couple whose surrogate underwent a hysterectomy, Johnson-Ellis wrote: “We have already told you that the insurance companies have been declining some of the claims and we are actively working with the broker to get this issue resolved but you should also consider that they may not be paid out and there is nothing we are able to do to change this …
“We appreciate this is not an insignificant sum but this genuinely is out of our control.”
Johnson-Ellis also said the company had switched insurance providers, writing: “We’re also managing this for 300 other journeys, which is a complex position to be in.”
Lawyers acting for My Surrogacy Journey said the company did not comment on individual cases, but that existing insurance policies were in place and claims continued to be accepted and processed.
They said the company understood that a small number of claims had been rejected and was supporting people seeking to resolve those claims with an insurer.
Under the surrogacy arrangements, intended parents are understood to be contractually required to cover medical costs not paid by an insurer.
The couple said they had been recommended the company’s Mexico option. Its website advertises that intended parents using the route can have a baby in “under 18 months”.
They said they were told the UK route could take up to five years and that the US option was much more expensive.
Lawyers for My Surrogacy Journey said prospective parents are given information about typical timelines, costs, legal frameworks and practical considerations, and that the 18-month timeframe is indicative only.
The couple said their surrogate developed placenta accreta, a serious condition in which the placenta attaches to the wall of the uterus.
Emails from Johnson-Ellis acknowledged that the insurance provider investigated the birth after the surrogate experienced health complications.
The parents are considering legal action, while the Guardian said it understood at least four other couples were reviewing their options.
Phil Brickell, MP for Bolton West, raised concerns in parliament about a separate couple who had used My Surrogacy Journey.
He said: “Two of my constituents recently travelled to Mexico, where their children were born by surrogacy.
“Those births were facilitated by a company called My Surrogacy Journey, which is listed on gov.uk.
“While in Mexico, they had repeated traumatic experiences with the company relating to issues including insurance for their children, accusations of bullying towards staff and repeated efforts to silence any constructive criticism.
“I understand that other members of this house have received similar complaints.”
Brickell called for My Surrogacy Journey to be removed from gov.uk pending a review by the Human Fertilisation and Embryology Authority.
Lawyers acting for My Surrogacy Journey said the company was communicating with DHSC and was confident any issues could be resolved.

Targeting CD1d altered immune cells slowed tumour growth and improved immunotherapy responses in mouse models of breast cancer, researchers found.
The findings suggest blocking the molecule could make the environment around breast tumours more favourable to anti-cancer immune responses.
Further work is needed to understand how these immune changes occur and how the approach could be safely used in patients.
Researchers from King’s College London, the Francis Crick Institute and University College London investigated how immune cells inside breast tumours influence cancer growth.
They focused on myeloid cells, a group of immune cells found in large numbers within tumours that can either support an immune attack against cancer or contribute to tumour growth and immune evasion.
The team examined CD1d, a molecule found on the surface of myeloid and other immune and tissue cells that helps regulate immune responses.
When CD1d was genetically removed from cells in a mouse model of breast cancer, the mice were more resistant to tumour growth. Researchers also saw changes in myeloid cell populations, including increased activity among cells that can help attack cancer.
The team then blocked CD1d using an antibody and again observed changes in myeloid cells and slower tumour growth. Blocking CD1d also improved responses to immunotherapy in the mouse model.
Researchers used single-cell RNA sequencing, a technique that examines gene activity in individual cells, to investigate the immune changes in more detail.
They identified a population of myeloid cells called monocytes that expressed genes associated with inflammation, an important part of the immune response. These cells were particularly important in restricting tumour growth in the mouse models.
A similar pattern of gene activity was identified in data from human breast cancer tumours. Its presence in myeloid cells was associated with positive responses to immunotherapy in breast cancer patients.
However, the findings in people were based on gene expression data and did not test CD1d-targeting treatment in patients.
Professor Patricia Barral, professor of immunobiology at King’s College London and senior author of the study, said: “Many breast cancers do not respond well to current immunotherapies.
“Our findings reveal a previously unrecognised mechanism by which immune cells within tumours are regulated.
“While CD1d is best known for helping immune cells recognise lipid molecules, we found that it also plays a role in shaping the behaviour of myeloid cells within tumours.
“These findings suggest that targeting the immune cells that surround and support tumours could boost anti-cancer immunity and potentially improve treatment responses in the future.”
Researchers now plan to investigate how the immune changes occur and how they can be safely harnessed in patients.
They also want to examine whether targeting CD1d could enhance existing treatments and influence treatment responses in different cancer types.
The work was supported by UKRI BBSRC, Breast Cancer Now and the Cancer Research UK City of London Centre.










 Menopause4 days ago
Menopause may not explain rising heart condition in women – study

 Fertility1 week ago
Paracetamol use may impact future fertility, studies suggest

 Sponsored Content2 weeks ago
Last chance to save on Women’s Health Week and Women’s Sport Summit: Early Bird pricing ends 11 September

 Insight4 days ago
Women with birth trauma face 2.5x higher healthcare costs – study

 Menopause2 weeks ago
Menopause hormone treatment may ease brain fog, study suggests

 Menopause1 week ago
Cancer drug could tackle osteoporosis menopause weight gain

 Cancer4 days ago
Study could explain why obesity is a breast cancer risk factor

 Diagnosis2 weeks ago
FDA approves AstraZeneca breast cancer drug