




Opinion
Pill problems: Why are women still struggling to access the right contraception and how can healthtech help?
By Lyndsay O’Brien, product owner at Phlo Connect


Contraception is the medical innovation that has the most pervasive impact on women’s lives, but it is also one of the most under-researched, under-innovated and under-resourced medical fields.
According to research carried out by Dama Health, 80 per cent of women experience contraception side effects that decrease their quality of life, and women try an average of four different methods during their fertile years.
“On average, most women spend almost half of their lives either trying to plan a pregnancy or to avoid unplanned pregnancies,” Dr Janet Barter, the president of the Faculty of the Royal College of the Obstetricians and Gynaecologists, said in Davina McCall’s recent contraception documentary.
The documentary shone a light on the barriers that women face in accessing the education and support that they need to make informed choices about their contraception. These include a poor understanding of how the side effects of different pills impact different women, a worrying prevalence of myths and misinformation, and a broken and costly medication access model.
The dominant message was that to improve women’s health outcomes in the UK, their struggle to access the right contraception must be solved.
National funding a “drop in the ocean”
In March, the UK government announced a £25 million investment over the next two years, as part of the Women’s Health Strategy for England. It said that the money will help to create “women’s health hubs” that “improve access and quality of care” for services, including contraception. The hubs promise shorter waiting lists and fewer health inequalities.
However, according to McCall, that could be a “drop in the ocean” in the context of cuts worth a billion pounds from health budgets in recent years, and her documentary suggests it may take years for women in the UK to reap the benefits of the government’s investment.
Women’s health VIMPROs are stepping up to provide solutions
Displaying the responsiveness and agility that is characteristic of vertically integrated micro providers (VIMPROs) in healthtech, a cluster of women’s health start-ups are trailblazing technology-first solutions.
These VIMPROs have identified women’s contraception pain points and built the technologies and infrastructures to address these. These technologies are streamlined, end-to-end solutions designed to meet the needs of a time-poor, price-sensitive, digitally savvy generation of women.
Navigating the contraception maze
If women are to be empowered to make informed decisions about contraception and reproductive health, they must have access to relevant knowledge and information. This is an area where VIMPROs are already delivering excellent results.
For example, Phlo Connect partner, The Lowdown, is a contraceptive advice and support platform which was created as a space for women to share their experiences with pills, coils and implants – later evolving into a contraception advice and prescription platform because of the huge demand for reliable information.
Dama Health, who were featured in the McCall documentary, are leading the research side of the education movement. Their team of scientists, gynaecologists and female health specialists is investigating how different female bodies respond to different types of contraception in the short term and long term.
They are using the findings, and their own advanced technology and biomarkers, to deliver women with personalised and informed contraceptive support via a digital interface.
Bridging access gaps
VIMPROs are also successfully leading the charge when it comes to building bridges that link up every step of women’s contraception journey.
Most women have been through the arduous process of going to their GP for a contraceptive pill prescription, then waiting for this to be filled by the pharmacy, and repeating the process all over again when they run short. They may have also experienced the stress of obtaining emergency contraception from their local clinic – something no woman should have to endure.
That’s why Hello Eve was created: to put an end to unnecessary expense, inconvenience and awkwardness. Their online contraception platform acts as a “one-stop-shop” for women, where they can consult with a clinician, choose the right treatment personalised to their needs, and arrange discrete, affordable delivery to a location of their choice.
To fix the frustrating fragmentation of the prescribing process, Hello Eve leverages the Phlo Connect technology stack. Using Phlo Connect APIs, Hello Eve’s clinicians can access true digital prescribing and medication dispensing that is secure, compliant and traceable at every stage.
Collaborative innovation at scale
Dr Geeta Kumar, the vice president of the Royal College of Obstetricians and Gynaecologists, said in response to the McCall documentary that contraception was a “vital part of sexual and reproductive rights for women”.
It follows that by meeting women’s sexual and reproductive rights, every innovation and collaboration in the field of contraception will positively impact on women’s health and wellbeing outcomes. Thus, the importance of women being given access to timely, convenient digital advice and contraception delivery from the privacy of home cannot be underestimated.
As explored above, partnerships between women’s health advocates, research teams, VIMPROs and digital pharmacy infrastructure providers have begun to lay the groundwork for a contraception revolution.
With continued investment, the scale and reach of their efforts will soon expand to empower every woman with seamless, digitally-mediated access to optimal reproductive health.
Lyndsay O’Brien is product owner at London-based digital pharmacy infrastructure company Phlo Connect.











A new clinical study has found that an at-home device for tracking reproductive hormones can identify ovulation with an accuracy that closely matches hospital-grade ultrasound scanning, in what researchers describe as a significant step for women’s health technology.
The findings, published this week in Reproductive BioMedicine Online, come from an 18-month trial led by Dr Thomas P. Bouchard that followed 121 ovulatory cycles and included 890 transvaginal ultrasound scans.
The study compared results from the Mira at-home hormone monitor, which tracks four hormones through urine samples, against the two methods long considered the clinical gold standard: ultrasound-confirmed ovulation and blood serum testing.
Researchers found that the day of ovulation, as confirmed by repeated ultrasound scans, fell within a day of the peak in luteinising hormone (LH) detected by the device in 96 per cent of cycles studied.
A new benchmark after 25 years
The study’s authors say it represents the first time a quantitative, multi-hormone at-home monitor has been validated against blinded ultrasound scanning under STARD guidelines, the internationally recognised standard for reporting diagnostic accuracy research.
Existing consumer fertility trackers, they note, have largely relied on simpler yes/no hormone readings or date-based algorithms that have gone unchanged for a quarter of a century.
The device tracks four hormones: LH, the oestrogen metabolite E13G, the progesterone metabolite PDG, and follicle-stimulating hormone (FSH).
What the data showed
Alongside the headline ultrasound comparison, researchers reported several other findings:
- Blood test correlation: readings from first-morning urine samples closely tracked blood serum levels drawn within 90 minutes, with the strongest correlation for LH, followed by progesterone and oestrogen metabolites, and a weaker but still notable link for FSH.
- Hidden variability in “regular” cycles: even among participants with typically regular periods, 11 per cent of cycles were found to be anovulatory, meaning no egg was released. In a further 12.4 per cent of cycles, ovulation occurred while LH was still climbing rather than after it peaked – a pattern researchers say calendar-based apps and single-day tests would likely miss.
- Earlier warning of fertility window: rising oestrogen signals were detectable roughly five to six days before ovulation, reflecting the natural development of ovarian follicles and offering an earlier indication of the fertile window than LH tracking alone.
‘Precise biological data without the clinic visits’
Dr Bouchard, the study’s lead author, said the research set a new bar for evaluating consumer fertility devices.
“For over two decades, at-home fertility tracking was based on qualitative indicators without providing quantitative hormone values,” he said, adding that testing the device against nearly 900 ultrasound scans under a blinded protocol gave the field a rigorous new benchmark.
Sylvia Kang, founder and chief executive of Mira, said the results pointed to a broader shift in how reproductive health could be monitored.
“Women deserve precise biological data about their reproductive health without needing constant clinic visits and serial blood draws,” she said, describing the findings as evidence that at-home testing could deliver “clinic-grade hormonal visibility.”

Sahar Abid is a Science Associate at Ema EQ, where she works on cultural sensitivity and bias in AI.
A woman asks an AI health assistant about postpartum depression.
She mentions that her in-laws are telling her to “push through” and skip medical help, even as her symptoms get harder to manage. She never says where she is from or names her background.
The assistant describes the condition and gives her a hotline number. It sounds correct, but it misses what she needs.
That gap is more common than the industry admits, and it points to a blind spot in how we test health AI for bias.
Most bias testing looks at what people explicitly say.
The typical way to check an AI for bias is to label a prompt with someone’s demographic details and see if the answer changes. That catches some problems but misses a bigger one.
Most people do not lead with their identity. They lead with their situation. The woman above told the assistant everything it needed to help her, just not in the form of a label.
Her real question was not only “what is postpartum depression?” It was “how do I get care when the people around me don’t want me to?
When family members hold sway over health decisions, and in many communities they do, advice that asks someone to overrule their family is not something they can act on.
The AI didn’t say anything factually wrong. It answered a different question than the one she was living.
We call this culturally implicit bias, meaning the AI misses the cultural context a situation implies rather than the context a person spells out.
When systems are trained to notice only the explicit cues, they fall back on a default answer built for the majority. For everyone else, the response can feel generic, off-target, or discouraging enough that they stop looking for help.
In health, that is not small. The people most likely to be missed are often the ones the system already underserves.
What we set out to test.
At Ema, we wanted to know how well AI picks up on cultural context that is implied but never stated. So we built our own way to test for it, across a range of communities and real situations like postpartum depression and fertility, using questions that carried cultural meaning without announcing it.
The patterns were consistent. Models often missed the meaning underneath the question. They dropped the specific details a person did share and smoothed them into something generic.
And even when they pointed toward real care, they tended to offer one option instead of choices that might actually fit a person’s life. Any one of those can be the difference between someone following the advice and walking away from care.
Why this matters for anyone building health AI.
Getting this right is the right thing to do, and it also works better.
When an answer reflects a person’s real context, people trust and act on the recommendations more, so they get the help and support they need.
Testing for it is harder than the shortcut most teams use. Swapping a name or a demographic label in and out is easy. Checking whether a model actually understands the human context around a question takes more care.
The shortcut teaches models to perform cultural competence instead of practicing it. No matter how much or how little someone chooses to share, they deserve an answer that is warm, complete, and usable.
A better question.
The bar for equitable health AI should be “does it serve someone who never told you who they are?” It is the harder test, but it determines whether real people get help.
The work of getting there is far from finished, and it is exactly what we are building toward at Ema.
Sources: Naidoo, V., & Chadha, K. K. (2025), Culturally responsive AI chatbots: from framework to field evidence, Computers in Human Behavior: Artificial Humans. Souligne, N., & Subbian, V. (2026), FairLogue: A toolkit for intersectional fairness analysis in clinical machine learning models.


A perimenopause app that maps existing smartwatch data to the menopausal transition has launched across 39 markets in the UK and Europe.
anna app uses information already recorded by wearables, including sleep, heart rate and body temperature, and returns one suggested lifestyle action each morning alongside the research behind it.
The company says each rule in its library links a defined pattern in a woman’s own data to a specific action. The recommendations were developed with an advising clinician and draw on more than 300 published studies.
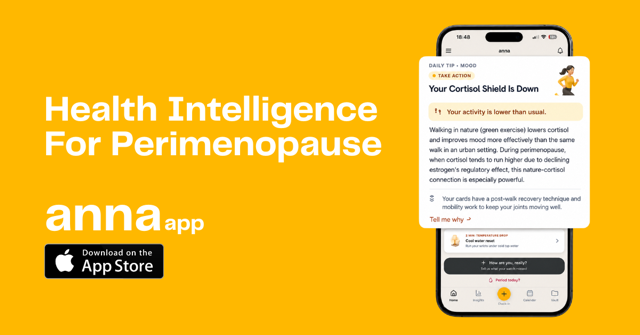
The company says recommendations are not generated automatically and each can be traced to research reviewed by a doctor.
The app was built by two women in Riga, has been funded without outside investment and was tested with women in the UK over three months before launch.
Perimenopause is the period of hormonal change before periods stop and usually begins after 40.
The company says one of the challenges is the unpredictability of the transition, with sleep, energy, mood and concentration potentially changing from week to week.
Because the experience varies between women, the developers say it can be difficult to find care tailored to individual needs. After 45, there is also no reliable blood test to confirm perimenopause.
The transition can coincide with a busy period in women’s working lives.
CIPD research published in 2023 found that 27 per cent of working women aged 40 to 60 with menopause symptoms said they had affected their career progression, equivalent to around 1.2m women in the UK.
Some 79 per cent said they felt less able to concentrate.
The long-running Study of Women’s Health Across the Nation, which has followed thousands of women through the menopausal transition, found that cognitive difficulties reported during perimenopause appear to be time-limited, with improvement returning in early postmenopause.
The developers say anna differs from standard wearable data by interpreting measurements specifically in the context of perimenopause.
A smartwatch may show changes in sleep, heart rate or temperature, but anna is designed to look at combinations of those signals and link them to lifestyle guidance for that day.
The app is also designed to work without daily symptom logging.
Users can complete an optional daily check-in if they want to add more context, but the app can operate without a symptom diary or daily manual entries.
It uses information from a compatible device the user already owns, such as a watch, ring or band.
Elina Pika-Lepere, co-founder and chief executive of anna app, said: “Perimenopause arrives exactly when a woman has the least spare capacity. She is often at the peak of her career, raising children, caring for ageing parents. What she has lost is not information, it is predictability.
“We built anna to offer a helping hand and evidence-based guidance through a stage that is difficult but temporary.”
The company gave the example of a morning when a user’s watch shows she has slept well below her own 28-day average.
Rather than simply telling her she is tired, anna may suggest choosing one priority and working on it in 25-minute blocks with a short break between them.
The app also displays the sleep and concentration research used for the recommendation.
anna was founded by Pika-Lepere, who spent 15 years building products in advertising, retail and e-commerce, and product lead Zanda Freimane, whose background is in product management in fintech and e-commerce.
The wider team includes a mathematician and university researcher advising on data architecture, a senior developer and a user experience adviser from a Baltic unicorn company.
anna app is not a medical device and does not provide medical advice.
Its guidance is limited to lifestyle support, and the company describes the app as a tool to complement a doctor rather than replace professional medical care.
anna app is available on iOS across 39 markets in the UK and Europe and is listed on the App Store as anna: Perimenopause & Sleep.
The app is in English and works with Apple Watch, Garmin, Fitbit, Oura and Whoop through Apple Health.
The company says user data is hosted in the EU and is never sold.
The service costs £13.99 a month or £99.99 a year in the UK and €14.99 a month or €99.99 a year in the euro area after a seven-day free trial.








 Diagnosis1 day ago
Trust to decide how far back to review unnecessary breast cancer surgeries

 Cancer2 days ago
New test could cut need for invasive womb cancer checks

 Healthy ageing4 days ago
Higher BMI in early adulthood linked to lower breast cancer risk after menopause

 Business & startups3 days ago
Personalising women’s health with AI

 Pregnancy1 day ago
UK commits £254m to boost women’s maternal healthcare choices

 News4 days ago
EU healthcare’s gender pay gap hits 19%, WHO report finds
 Menstrual & gynaecological health3 days ago
Mira launches at-home cortisol tracking kit

 Diagnosis3 days ago
Targeted nanotherapy shows endometriosis promise
Pingback: FDA approves first over-the-counter birth control pill - FemTech World