




Diagnosis
Smear test: Everything you need to know before your appointment

Article produced in association with Spital Clinic
Cervical screening saves thousands of lives from cervical cancer in the UK every year.
The programme has changed significantly in recent years, and understanding what it now involves — and what your results actually mean — is probably the most useful preparation you can do before your appointment.
Why Cervical Screening Exists — and What Changed in 2025
The NHS cervical screening programme now uses HPV primary screening — a method NHS England describes as testing for the human papillomavirus (HPV) rather than looking directly for abnormal cells.
If HPV is not found, the sample is not examined further; if HPV is found, the same sample is then checked for cell changes.
The reason HPV sits at the centre of this approach is straightforward. Nearly all cervical cancers are caused by certain high-risk types of HPV — and HPV is extremely common.
Most people encounter some form of it during their lives, and the body usually clears it without any treatment.
The problem arises when high-risk HPV persists, because over time it can cause cell changes in the cervix that, if left undetected, may eventually develop into cancer.
Cervical screening is therefore a prevention test, not a cancer diagnosis. Its purpose is to find those cell changes early, when treatment is straightforward and effective.
A significant change took effect in England on 1 July 2025.
The screening interval for those aged 25–49 was extended from three years to five years, in line with the 50–64 age group — so everyone aged 25 to 64 in England is now invited every five years.
The interval in Northern Ireland currently differs; Cancer Research UK has current details.
Who Is Invited and How to Book
NHS England invites everyone with a cervix aged 25 to 64, with the first letter usually arriving a few months before a person’s 25th birthday.
Invitations are sent automatically and are linked to GP registration — the simplest way to make sure yours arrives is to be registered with a GP and keep your contact details up to date. If your invitation hasn’t come through, any GP surgery can arrange an appointment.
Trans men and non-binary people registered as female with their GP will receive invitations automatically.
Those registered as male will not — but can self-refer through the NHS cervical screening programme website or ask their GP to arrange a test.
People over 65 are not routinely invited but are not excluded.
Anyone who has never been screened, or whose most recent result was abnormal, can request screening through their GP or a clinic.
Appointments are most commonly offered at GP surgeries, carried out by a nurse or doctor.
For those who prefer a different setting, shorter waits, or an appointment outside NHS hours, a private smear test can be arranged through specialist gynaecology clinics, often within a few days.
What Happens at a Smear Test Appointment
The test itself takes less than five minutes, with the full appointment lasting around ten minutes.
Knowing what happens — step by step — removes most of the uncertainty that makes it feel more daunting than it actually is.
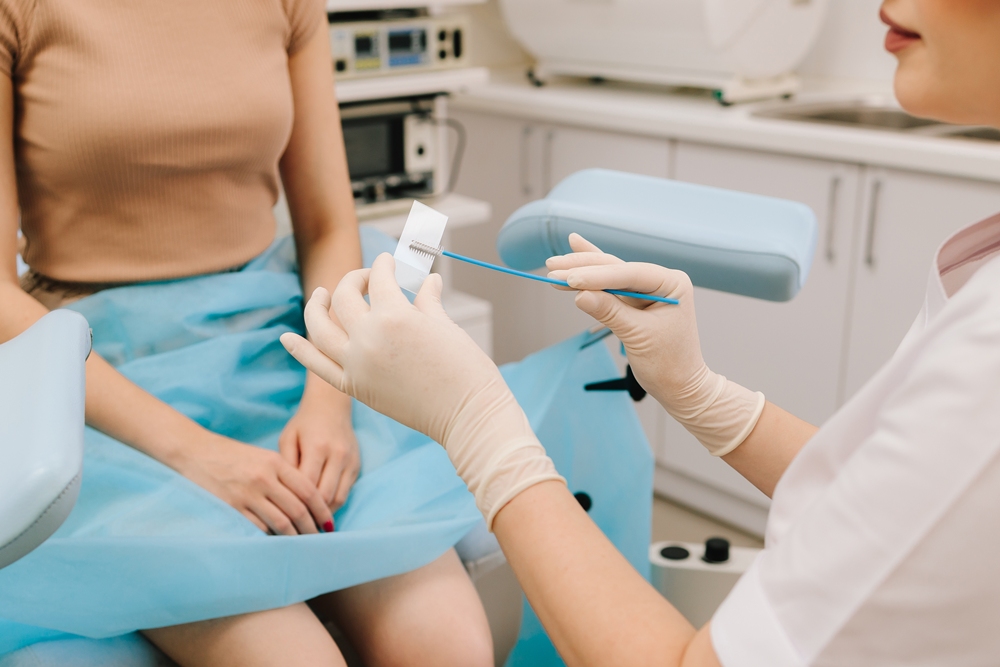
You undress from the waist down and lie on an examination table, knees bent and falling gently apart.
The nurse or doctor applies a little lubricant and gently inserts a small speculum, which is opened just enough to make the cervix visible.
A small, soft brush sweeps a cell sample from the surface of the cervix. The speculum is removed, and you get dressed.
That is the entirety of the test.
A little preparation helps both comfort and sample quality.
Avoid vaginal medicines, lubricants, and creams for at least two days beforehand, as residue can interfere with the results. Avoid scheduling during your period for the same reason.
Loose-fitting clothing — a skirt or wide-leg trousers — makes undressing and repositioning much easier.
If you are going through the menopause, vaginal dryness can make speculum insertion uncomfortable.
Cancer Research UK notes that using a short course of oestrogen cream or pessaries for around two weeks beforehand can help considerably — though stop two days before the appointment to avoid affecting the sample.
It is worth mentioning to your GP when you book.
Most people feel some pressure or mild discomfort, but it does not usually hurt.
If you find it painful, you can ask for a smaller speculum, insert it yourself, or try lying on your side — all are standard adjustments. Light spotting afterwards is normal and usually clears within a few hours. You can ask to stop at any point.
Understanding Your Results
The most common result — received by 87 in every 100 people screened — is HPV not found.
That means no high-risk HPV was detected, your risk of developing cervical cancer before the next screen is very low, and nothing further is needed until your next invitation arrives in five years.
The other results fall into two categories. Nine in every 100 people are told HPV was found, but no cell changes were detected.
This is not a cancer result and does not require immediate treatment — it means high-risk HPV is present and the cervix is being monitored.
The pathway is a repeat screen at one year; if HPV is still present, another repeat at two years. Only if it persists at that point is a colposcopy referral made.
Four in every 100 people receive an HPV-positive result alongside detected cell changes, and are referred directly for colposcopy.
That referral is not a diagnosis of cancer.
A colposcopy is a closer examination of the cervix, carried out in a clinic using a magnifying device, allowing a clinician to look in detail at any flagged cell changes.
Most people who attend colposcopy do not have cervical cancer — NHS England is clear on this. If a biopsy is taken or cells are removed, there is a small risk of bleeding and infection, both well-managed.
Those who prefer not to wait for an NHS appointment can access a private colposcopy at specialist clinics.
Results usually arrive by post or through the NHS App within two to six weeks. Samples are kept for ten years.
HPV can remain in the body for many years without symptoms, so a positive result says nothing about recent exposure or transmission history.
HPV, the Vaccine, and When to See a GP Without Waiting
Nearly all cases of cervical cancer are linked to high-risk HPV.
The virus spreads through skin-to-skin genital contact, vaginal, anal or oral sex, and sharing sex toys — it does not require penetrative sex to pass between people. The vast majority of people who carry it clear it naturally and will never know they had it.
The UK’s HPV vaccination programme, which began in 2008, has meaningfully reduced risk in younger age groups.
But vaccinated people still need to attend cervical screening — the vaccine does not protect against all high-risk HPV types. Vaccination and screening work together; one does not replace the other.
Cervical screening runs on a schedule, but some symptoms need attention straight away — do not wait for your routine invitation.
According to NHS England, these include unusual vaginal bleeding, bleeding after sex, bleeding during or after the menopause, heavier periods than usual, changes in vaginal discharge, pain during sex, or persistent lower back or pelvic pain.
These symptoms do not confirm anything, but they need investigating without delay.
Attending every invitation remains the single most important thing anyone in the eligible age group can do — and with the 2025 extension to five-year intervals, each appointment now covers a longer window than it once did.
The extension of the English screening interval to five years is backed by strong evidence about the accuracy of HPV primary screening.
Simply turning up remains, by some margin, the most protective thing anyone in the eligible age group can do.
This article is for informational purposes only and does not constitute medical advice. For personal health concerns, consult a qualified healthcare professional. Cervical screening eligibility and intervals may vary; refer to current NHS guidance or your GP for the most up-to-date information applicable to your circumstances. This piece was produced in association with Spital Clinic, which provided background clinical information for editorial purposes. Hyperlinks to external sources are included for reference only and do not represent an endorsement of any product, service or organisation.















Menopause is often absent from women’s electronic health records, a study of nearly 396,000 women has found.
Researchers found menopause appeared almost seven times more often in participant surveys than in electronic health records (EHRs).
The findings suggest important reproductive health information, including age at menopause, may often be missing from health records used for research.

Audrey Hendricks, associate professor of bioinformatics at CU Anschutz and the study’s principal investigator, said: “Ultimately, we cannot study what we do not measure. We cannot treat what we do not know.
“Menopause has enormous implications for women’s health, but if we don’t consistently capture when menopause occurs and other important reproductive health information, we limit our ability to understand how this transition affects disease risk and health outcomes.”
Researchers at the University of Colorado Anschutz analysed data from women taking part in the National Institutes of Health’s All of Us Research Program.
They compared menopause information reported by participants in surveys with menopause diagnoses recorded in their electronic health records.
Around 193,000 menopause observations were identified in survey data, compared with approximately 28,000 diagnoses in EHR data.
Menopause was documented in electronic health records for only about 7 per cent of women in the dataset.
Nearly all participants with a menopause diagnosis recorded in their EHR also reported menopause in survey data. However, substantially fewer women had menopause documented in their health records.
Other important information was also frequently unavailable, including age at menopause, which researchers may use when examining links between menopause and chronic disease risk.
Menopause is a physiological transition that can affect cardiometabolic health and many other aspects of women’s health.
Researchers said relatively little is known about how factors including the timing and type of menopause influence health outcomes across diverse populations.
Large-scale programmes such as All of Us combine participant surveys, electronic health records and genomic data, but menopause-related research depends on relevant reproductive health information being available.
Missing menopause information can make it harder to investigate how the transition relates to health and disease.
The findings may also help researchers using All of Us data define menopause-related study populations, design studies and estimate how many participants are needed.
Hendricks said: “We have an enormous opportunity to use large-scale datasets to understand women’s health across the menopause transition and to identify who may be at greater risk for disease.
“But we need to make sure that the information researchers need is actually being collected.
“We must do a better job of capturing women’s health information, including reproductive health and measures related to menopause.”
Researchers said more complete and consistent collection of menopause and reproductive health information could help future studies examine factors such as age at menopause and their relationship with disease risk and health outcomes.











 Menopause4 days ago
Menopause may not explain rising heart condition in women – study

 Fertility1 week ago
Paracetamol use may impact future fertility, studies suggest

 Entrepreneur2 weeks ago
Last chance to save on Women’s Health Week and Women’s Sport Summit: Early Bird pricing ends 11 September

 Insight4 days ago
Women with birth trauma face 2.5x higher healthcare costs – study

 Menopause2 weeks ago
Menopause hormone treatment may ease brain fog, study suggests

 Menopause1 week ago
Cancer drug could tackle osteoporosis menopause weight gain

 Cancer4 days ago
Study could explain why obesity is a breast cancer risk factor

 Diagnosis2 weeks ago
FDA approves AstraZeneca breast cancer drug